8 Early Symptoms of Acoustic Neuroma That Often Go Unnoticed
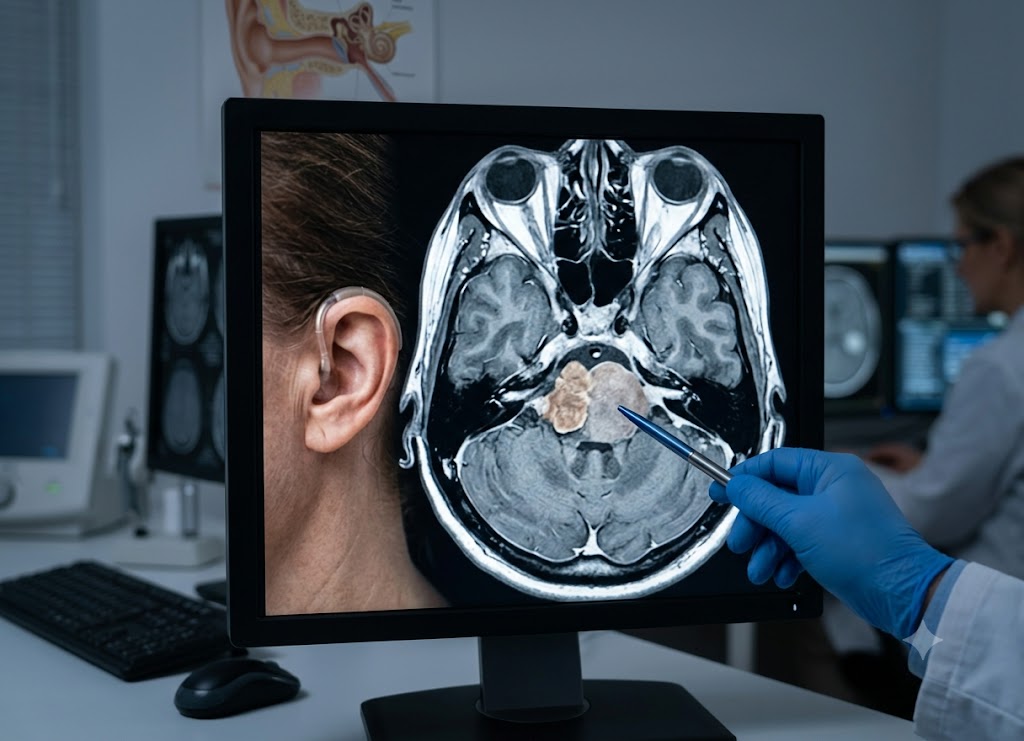
Acoustic neuroma is a non-cancerous tumor that grows on the vestibular nerve, the nerve that sends hearing and balance signals from the inner ear to the brain. Doctors also call it vestibular schwannoma. Because it grows so slowly, its symptoms are easy to blame on age, stress, earwax, an ear infection, or plain dizziness. The most common early clue is hearing loss in just one ear, but the change is so gradual that many people brush it off.
Early signs look a lot like everyday inner ear problems: ringing in one ear, mild dizziness, a blocked feeling in the ear, headaches, facial numbness, or slight clumsiness. None of these feels alarming on its own. The real warning is when symptoms affect one side more than the other and refuse to go away or keep getting worse. This article covers eight early symptoms that are often missed and explains why a doctor should check them.
What is an Acoustic Neuroma?
An acoustic neuroma is a slow-growing, benign tumor that forms from Schwann cells, the cells that wrap around the eighth cranial nerve (the vestibulocochlear nerve). This nerve links the inner ear to the brain.
The medical name, vestibular schwannoma, is actually more accurate. The tumor usually starts on the balance (vestibular) part of the nerve, not the hearing (acoustic) part. Even though it is benign, it can cause real trouble because it sits in a very tight bony space, the internal auditory canal, right next to vital brain structures. As it grows, it presses on the nerve and causes the classic trio: hearing loss in one ear, tinnitus (ringing), and dizziness or poor balance.
If it keeps growing into the space at the base of the brain called the cerebellopontine angle, it can press on nearby nerves and cause facial numbness or weakness. In the worst cases, it squeezes the brainstem and cerebellum, which can become life-threatening. The danger is not that it spreads like cancer. It is the pressure (“mass effect”) it puts on surrounding nerve tissue, which can lead to progressive damage.
1. Defining the Tumor Architecture
To understand this tumor, start with where it begins. The eighth cranial nerve has two working parts: the acoustic part, which carries sound, and the vestibular part, which carries balance information. The tumor almost always develops from Schwann cells around the balance part.
Although it is not cancerous, the tight space of the internal auditory canal makes its growth risky. As it enlarges, it crowds the nerve fibers and cuts down their blood supply.
Internal auditory canal (tight space)
   ├─ Early stage: stays inside the canal → pinches hearing and balance fibers → hearing loss in one ear
   └─ Late stage: spills into cerebellopontine angle → presses brainstem and cerebellum → disturbs fluid flow
Left unchecked, the tumor can outgrow the bony canal and enter the cerebellopontine angle. There it can press on other cranial nerves and the brainstem, turning a local ear problem into a serious neurological one.
2. Benign Pathology vs. Malignant Misconceptions
An acoustic neuroma is definitely not brain cancer. It is benign: it grows by pushing outward rather than invading tissue, and it cannot spread to other parts of the body. This sets it apart from aggressive cancers like glioblastoma, which invade and destroy healthy brain tissue.
The tumor cells are well-formed and enclosed in a fibrous capsule. They divide very slowly, often growing only about one to two millimeters a year, which gives the brain time to adapt.
But benign does not mean harmless. The risk comes from location, not cell type. The skull base is rigid and packed with vital nerves, so even a slow-growing mass presses them against bone. If it grows large enough to push on the brainstem and cerebellum, it can block the flow of cerebrospinal fluid and cause hydrocephalus, a dangerous rise in pressure inside the skull. Chemotherapy is not used, but the condition still needs careful monitoring or treatment such as stereotactic radiosurgery or microsurgery.
3. Cellular Mechanisms and Genetic Drivers
The tumor comes from an overgrowth of Schwann cells. These cells normally act like electricians of the nervous system, wrapping nerve fibers in myelin, the fatty insulation that lets signals travel quickly.
About 95% of cases are sporadic, meaning they appear on one side only and are not linked to lifestyle or environmental toxins. Research points to a mutation in a gene on chromosome 22.
Faulty gene on chromosome 22 → low levels of merlin protein → Schwann cells multiply unchecked
This gene makes a protein called merlin, which acts like a brake on Schwann cell growth. When the gene is damaged in a single cell line, the brake fails and the cells multiply until a tumor forms.
The other 5% or so are inherited through a condition called Neurofibromatosis type 2 (NF2). In NF2, every cell in the body carries the faulty gene. Its hallmark is tumors on both hearing and balance nerves, and people with NF2 are also at higher risk of other benign tumors such as meningiomas and spinal ependymomas, so they need lifelong specialist care.
4. Clinical Presentation and Symptom Evolution
Early symptoms tend to creep in quietly, and people often put them down to aging or a stuffy sinus. The classic first sign is a slow, unexplained loss of hearing in one ear, caused by pressure on the auditory nerve fibers.
Up to 80% of patients also have tinnitus in the same ear: a constant ringing, buzzing, or hissing. You might expect strong spinning vertigo, since the tumor starts on the balance nerve, but the growth is so slow that the brain adjusts. Most people feel only a vague unsteadiness or mild disorientation.
Early (canal) phase: uneven high-pitch hearing loss, constant one-sided tinnitus, mild unsteadiness
Advanced (angle) phase: facial numbness (CN V), twitching or weakness (CN VII), headache, nausea, blurred vision
Once the tumor moves into the cerebellopontine angle, neighboring nerves get involved. Pressure on the facial nerve can cause twitching, a lopsided smile, or muscle weakness. Pressure on the trigeminal nerve can cause facial numbness, tingling, or a weaker blink reflex. In advanced stages, a large tumor presses on the brainstem and cerebellum, changing the way a person walks, causing constant headaches, and making urgent treatment necessary.
8 Overlooked Early Signs of an Acoustic Neuroma
The eight commonly missed early signs are: hearing loss and tinnitus in one ear, mild balance problems, facial numbness or tingling, a feeling of fullness in the ear, changes in taste, trouble understanding speech, persistent headaches, and increased clumsiness.
Each one looks minor on its own, so it helps to see why they happen and why they get mistaken for something else.
1. Auditory Fluctuations and Sound Processing Deficits
Hearing changes are usually the first warning. Because they come on slowly, people blame age or earwax. But the ear itself is not failing. The auditory nerve is being squeezed inside the narrow canal.
Unilateral Hearing Loss and Asymmetric Tinnitus
The most common early sign is a slow drop in hearing clarity in one ear only. Age-related hearing loss usually affects both ears equally, so this one-sided pattern is a key clue for doctors. Often the first sounds to fade are high-pitched ones, like a child’s voice or a ringing phone. Up to 80% of people also get tinnitus in that ear, a steady ring, buzz, or hiss. It happens because the pinched nerve fires random signals that the brain reads as real sound.
One-sided nerve compression
   ├─ Volume loss: slow drop in high pitches, favoring the other ear, mistaken for aging
   └─ Signal distortion: random nerve firing, constant tinnitus, mimics a blocked ear
Advanced Phonemic Regression in Distracting Environments
Another easy-to-miss sign is trouble understanding speech, especially in noisy places like restaurants or gatherings. A person may pass a quiet-room hearing test yet struggle to follow words when there is background noise. They often feel that everyone is mumbling: they can hear the voice but not make out the words.
This happens because the damaged nerve cannot carry the fast timing signals needed to tell similar consonants apart. Good volume perception combined with poor word understanding is a classic sign of a problem behind the cochlea, which can point to a growing mass.
2. Spatial Disorientation and Subtle Motor Coordination Changes
Since the tumor usually starts on the balance nerve, balance is affected early. But the slow growth lets the body adapt, which hides how much damage there is.
Low-Velocity Dysequilibrium
Instead of the violent spinning of an inner ear infection or Meniere’s disease, this tumor causes a mild, constant unsteadiness. People describe it as being on a rocking boat, swaying slightly when standing still, or losing stability when they turn their head fast.
The brain compensates by leaning more on vision and body sensors, so the problem shows up in the dark or with eyes closed, like in a dim hallway or the shower. That is why it is so often written off as tiredness or low blood pressure.
Slow pinch on balance nerve → brain compensates → balance problem stays hidden
Asymmetric Clumsiness and Postural Drift
With less reliable balance information, some people become slightly clumsier on one side. It is not a serious loss of muscle control, just a small dip in spatial awareness. They might keep bumping a shoulder on a doorframe, misjudge distance when reaching, or drift to one side when walking straight.
The brain is working with slightly wrong information about head position and movement, so small errors creep into everyday actions. People usually laugh it off as carelessness, so this sign is rarely linked to a neurological cause.
3. Somatosensory and Neighboring Cranial Nerve Interactions
When the tumor grows out of the internal auditory canal into the cerebellopontine angle, it begins touching nearby nerves in this crowded area at the base of the skull. Symptoms then go beyond hearing and balance.
Crowding at the cerebellopontine angle
   ├─ Trigeminal nerve (CN V): on-and-off cheek numbness, lip tingling, mistaken for dental problems
   ├─ Facial nerve (CN VII): metallic or sour taste, front of the tongue affected
   └─ Fluid changes: constant ear fullness, mimics sinus congestion
Episodic Facial Numbness and Paresthesia
The trigeminal nerve runs close to the hearing pathway and gives feeling to the face, teeth, and jaw. When the tumor presses on it, you may notice occasional numbness or “pins and needles” on one side of the face, such as a brief loss of feeling in the cheek or around the lips. Because it comes and goes early on, people blame stress, dental trouble, or sleeping in an awkward position.
Unilateral Dysgeusia and Altered Taste
A less common but very specific early sign is a change in taste, called dysgeusia. It points to the facial nerve, which travels through the same narrow channel as the hearing and balance nerve. One of its branches, the chorda tympani, carries taste from the front two-thirds of the tongue.
When the tumor stretches or presses on these fibers, one side of the mouth may taste metallic, sour, or dull. Since the other side works normally and smell is unaffected, the change is hard to pin down and rarely connected to an ear or nerve problem.
Unyielding Aural Fullness
Many people feel constant pressure or stuffiness in the affected ear, like water is trapped in it or it is stuffed with cotton. Allergies and blocked Eustachian tubes cause similar feelings, but the difference here is that the fullness is constant and does not clear with yawning, swallowing, or popping the ears. It may result from changed fluid pressure in the inner ear or distorted pressure signals reaching the brain.
4. Mechanical Intracranial Pressure Markers
With a small tumor, headaches are uncommon. They become more likely as the tumor grows and pushes on nearby structures inside the skull.
Tumor growth → blocked cerebrospinal fluid flow → higher pressure in the skull → pain at the back of the head
As the mass enlarges, it can press on the cerebellum and the membranes that cover the brain, and eventually block fluid flow in the brain’s chambers. This can cause obstructive hydrocephalus and a slow rise in pressure.
The typical headache is a dull ache on one side of the back of the head. It is often worse in the morning after lying flat all night, and gets stronger with coughing, sneezing, or straining. Since headaches are so common, people blame stress or eye strain. That is why they should be judged alongside one-sided symptoms like hearing or balance changes.
What Happens After Suspecting an Acoustic Neuroma?
If symptoms suggest an acoustic neuroma, the next step is a thorough workup to confirm it, followed by a visit to specialists who decide the best plan for your case. Doctors also need to rule out conditions with similar symptoms, and the treatment options range from simply watching the tumor to active treatment.
1. The Definitive Imaging and Assessment Protocol
Diagnosis takes several steps. Because early symptoms build so slowly, doctors usually begin with specialized hearing and nerve tests before moving to advanced imaging.
Audiometric evaluation: finds nerve-related hearing loss, high-pitch gaps, poor word understanding
Contrast imaging: contrast dye highlights the tumor, measures size to the millimeter, checks pressure on the brainstem
First comes a full audiogram with an audiologist. It looks for asymmetric sensorineural hearing loss, where one ear is clearly worse than the other, especially for high-pitched tones.
If that pattern appears, the doctor may order an Auditory Brainstem Response test, which measures how fast signals travel from the inner ear to the brainstem. A delay on one side suggests a blockage or nerve problem and is a strong reason to move on to imaging.
The gold standard is an MRI of the brain and internal auditory canals with gadolinium contrast. While an audiogram hints at a nerve problem, the MRI shows the skull base in detailed 3D. The contrast agent travels through the blood and makes the tumor show up bright white against dark brain tissue. A skull base team, usually an otolaryngologist, a neurotologist, and a neurosurgeon, can then measure the tumor precisely, locate it, and judge how much it presses on the brainstem and facial nerve.
2. Clinical Distinctions: Differentiating Meniere’s Disease
Acoustic neuroma is often confused with Meniere’s disease because both involve the inner ear and can cause hearing loss, ringing, and balance trouble. A careful differential diagnosis is needed to get the right treatment.
Acoustic neuroma → slow Schwann cell growth → steady, constant unsteadiness
Meniere's disease → endolymph fluid buildup → sudden, severe episodes of vertigo
The main difference is the cause and how symptoms progress. A vestibular schwannoma is a physical tumor growing slowly on the nerve, so symptoms are steady and progressive over months or years. Meniere’s disease is not a tumor. It results from a buildup of endolymph fluid in the inner ear, and its symptoms come in episodes, with flare-ups followed by long calm periods.
The type of balance problem is the best clue. With a tumor, people usually feel mildly and constantly off-balance because the brain has adapted. In Meniere’s, attacks of intense spinning vertigo strike suddenly, last from twenty minutes to several hours, and often come with severe nausea and vomiting.
Hearing also differs. Tumor-related hearing loss declines steadily and rarely improves. In Meniere’s, hearing fluctuates: it drops sharply during an attack and partly recovers afterward, mainly in low frequencies, with a roaring tinnitus.
3. Genetic Transmission vs. Sporadic Occurrence
Medical data show a clear split between random mutations and inherited disorders. More than 95% of cases are sporadic, meaning they happen by chance with no family link. These tumors nearly always affect one side only and stay on that single nerve for life.
Sporadic (over 95%): random, non-inherited mutation, one ear only
Hereditary: linked to Neurofibromatosis type 2, autosomal dominant, tumors on both sides
The remaining cases come from Neurofibromatosis type 2, whose hallmark is tumors on the hearing and balance nerves on both sides of the head. NF2 is an autosomal dominant disorder caused by a mutation in the NF2 gene on chromosome 22, which makes the tumor-suppressing protein merlin.
When a parent passes on a faulty copy, the defective merlin cannot control cell division and Schwann cells grow unchecked. A child of an affected parent has a 50% chance of inheriting the mutation. This calls for lifelong monitoring for tumors in the nervous system, genetic counseling, and proactive care because the risk of total deafness in both ears is high.
4. Modern Management and Treatment Pathways
Once a contrast MRI confirms the tumor, a multidisciplinary team builds a personal plan. There is no one-size-fits-all choice. It depends on the tumor’s size and growth rate, the patient’s age and general health, and how severe the symptoms are.
Three options: Active surveillance | Stereotactic radiosurgery | Microsurgical removal
Active Surveillance (Watch and Wait)
For small, slow-growing tumors with few symptoms, doctors often suggest watching. It is common in older adults and people whose health makes treatment riskier than the tumor. Serial MRI scans, usually every six to twelve months, track growth. If the tumor stays stable and symptoms do not worsen, treatment is put off, sparing the patient the side effects of surgery or radiation.
Stereotactic Radiosurgery
This precise, non-invasive option suits small to medium tumors. With technology like Gamma Knife or CyberKnife, radiation oncologists send many tightly focused beams at the tumor from different angles. The aim is not to remove it but to damage the tumor cells’ DNA so they stop dividing, letting the tumor stabilize or shrink over time. It has a high success rate in stopping growth while keeping the risk to the nearby facial nerve low.
Microsurgical Intervention
Larger or fast-growing tumors, or those pressing hard on the brainstem, usually need direct surgical removal. A neurosurgeon or neurotologist performs a craniotomy and removes the tumor with specialized micro-instruments. The approach (translabyrinthine, retrosigmoid, or middle fossa) depends on the tumor’s size and location and on whether any hearing can be saved.
Surgery can cure the tumor completely, but it carries the highest immediate risks: permanent hearing loss, facial nerve weakness or paralysis, and complications like a cerebrospinal fluid leak. Each patient needs a careful risk-versus-benefit discussion.
Conclusion
Acoustic neuroma is easy to miss because early symptoms are mild, slow, and similar to other ear and balance problems. One-sided hearing loss, tinnitus, dizziness, balance trouble, ear fullness, headaches, facial numbness, and clumsiness can all be warning signs. The biggest clue is often asymmetry, when symptoms are stronger on one side. If they last, get worse, or start interfering with daily life, see a doctor to find the cause and choose the right treatment.
Frequently Asked Questions
1. What is acoustic neuroma?
It is a non-cancerous tumor that grows on the vestibular nerve between the inner ear and the brain. Since this nerve handles hearing and balance, symptoms usually affect one ear or one side of the body. It is also called vestibular schwannoma. It generally grows slowly, but it can cause serious problems if it gets big enough to press on nearby nerves or brain structures.
2. What is usually the first symptom of acoustic neuroma?
Most often it is gradual hearing loss in one ear. Some people notice ringing (tinnitus) before they realize their hearing has changed. Balance problems or dizziness can also appear early but tend to be subtle. Since these symptoms fit many ear conditions, the tumor is easy to miss at first.
3. Can acoustic neuroma cause dizziness or balance problems?
Yes. Because the tumor affects the vestibular nerve, which tells the brain about body position and movement, it can cause dizziness, unsteadiness, or trouble walking steadily. It may feel like lightheadedness or being off-balance. Some people adapt without noticing, which makes the problem harder to spot early.
4. Is acoustic neuroma cancer?
No, it is usually a benign tumor. But benign does not always mean harmless. As it grows, it can affect hearing, balance, facial sensation, or nearby brain structures. Regular monitoring matters because treatment depends on the tumor’s size, growth rate, symptoms, and the patient’s overall health.
5. How is acoustic neuroma diagnosed?
Usually with hearing tests and imaging. A doctor may order an MRI to look for a tumor near the inner ear and brain, and balance testing may be added if there is dizziness or unsteadiness. Early diagnosis helps doctors choose between observation, radiation therapy, or surgery when needed.