What is Appendicitis? Pain Location, Symptoms and Treatment
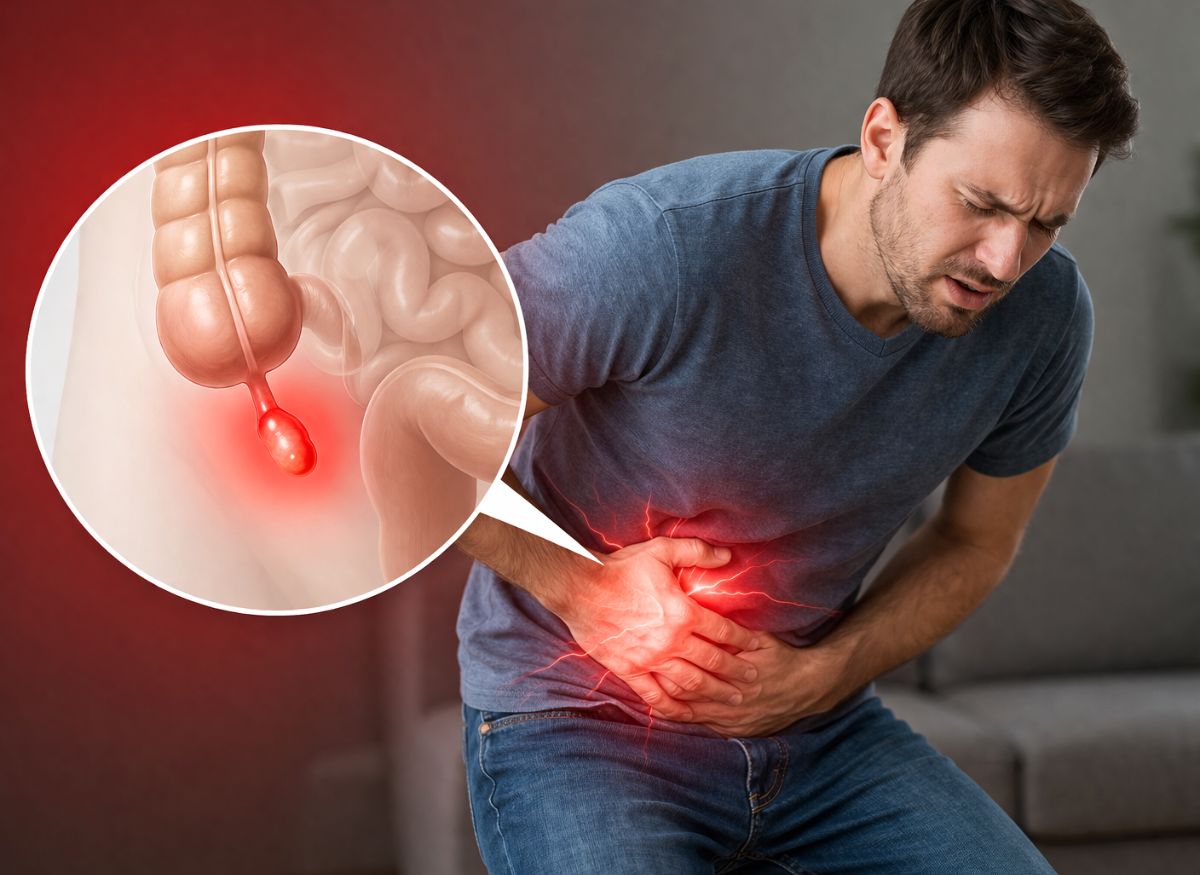
Appendicitis is among the most frequent surgical emergencies seen in clinical practice, yet it often starts with symptoms that appear deceptively minor.
Many patients first write off their early discomfort as plain indigestion, only to come back hours later in severe pain that needs urgent surgery.
This pattern shows how fast appendicitis can advance, and why recognizing it early is so important.
What Is Appendicitis?
Appendicitis is inflammation of the appendix, a small, tube-shaped structure attached to the cecum in the lower right part of the abdomen.
The appendix isn’t essential for survival, but when it becomes inflamed it can cause serious complications, including rupture and infection throughout the abdominal cavity.
With prompt diagnosis and treatment, outcomes are excellent. Delays, however, raise the risk of complications considerably.
Where Is the Appendix?
The appendix is a narrow tube, closed at one end, roughly 6 to 10 cm long. It branches off the cecum, the first section of the large intestine, and usually sits in the right lower quadrant of the abdomen.
Its precise position can vary, though:
- Retrocecal (behind the cecum)
- Pelvic
- Subcecal
- Pre-ileal or post-ileal
These differences can change how symptoms appear, sometimes making diagnosis harder.
Structurally, the appendix holds lymphoid tissue, which is especially plentiful in children and young adults. Although its exact role isn’t essential, it is believed to contribute to:
- Immune response
- Maintenance of gut microbiota
Even so, removing the appendix doesn’t cause significant long-term health problems.
Epidemiology
Roughly 7 to 8% of people develop appendicitis at some point in their lives. It is most common between ages 10 and 30 but can strike at any age.
- Slightly more common in males than in females
- A leading cause of sudden abdominal pain requiring surgery
- Incidence has stayed fairly stable, although imaging has improved diagnostic accuracy
Earlier diagnosis has substantially lowered complication rates in modern clinical settings.
What Causes Appendicitis?
Appendicitis most often arises when the lumen (the hollow interior) of the appendix becomes blocked, setting off a chain of inflammation, bacterial overgrowth, and rising pressure inside the organ.
Blockage is the main mechanism, but several factors can contribute to it.
Primary Causes
Luminal obstruction is the central event in how appendicitis develops.
Once the lumen is blocked, mucus builds up, pressure climbs, and bacteria multiply, leading to inflammation.
Common causes of blockage include:
- Fecaliths (appendicoliths): Hardened fragments of stool are the most frequent cause in adults. They can lodge in the appendix and physically block its opening.
- Lymphoid hyperplasia: Swelling of the lymphoid tissue in the appendix, often after a viral infection, is a common cause in children and teenagers.
- Foreign bodies or parasites (rare): Swallowed indigestible material or parasitic infections can occasionally block the lumen, but these causes are uncommon.
Contributing Factors
Beyond direct blockage, several factors may raise the chance of developing appendicitis:
- Infections (viral or bacterial): Gastrointestinal or body-wide infections can stimulate lymphoid tissue, causing swelling and possible obstruction.
- Low-fiber diet: Too little fiber may promote constipation and fecalith formation, indirectly raising risk.
- Family history: The role isn’t firmly established, but some studies suggest a modest genetic tendency in certain people.
Pathophysiology
Appendicitis unfolds in a predictable sequence, beginning with luminal obstruction and moving through inflammation and ischemia to, if untreated, perforation.
- A blockage of the lumen (for example, a fecalith or lymphoid hyperplasia) stops mucus from draining normally.
- Ongoing secretion raises pressure inside the appendix, causing it to swell.
- The rising pressure impairs venous outflow, leading to venous congestion and reduced blood supply.
- As ischemia sets in, the protective lining breaks down, allowing bacteria to overgrow and invade.
- This triggers inflammation and edema in the appendix wall, worsening the obstruction.
Without treatment, the process advances to:
- Ischemic necrosis (tissue death) of the appendix wall
- Perforation, typically within 24 to 72 hours, spilling infected contents into the peritoneal cavity
- Possible progression to a localized abscess or widespread peritonitis
This step-by-step course explains why symptoms evolve from vague discomfort to localized, severe abdominal pain.
Clinical Presentation
Early Symptoms
At first, symptoms are often nonspecific and stem from stimulation of visceral nerves:
- Periumbilical pain: typically dull and poorly localized
- Loss of appetite: frequently one of the earliest and most consistent features
- Nausea, with or without mild vomiting: usually appearing after the pain begins
Because these symptoms are so subtle, they are often mistaken for a minor stomach bug.
How the Pain Progresses
Once inflammation reaches the parietal peritoneum (the lining of the abdominal wall), the pain becomes more localized and more distinctive:
- Pain moves from around the navel to the right lower quadrant
- It settles at McBurney’s point, a key diagnostic landmark
- It becomes sharper, constant, and more intense
- It worsens with movement, coughing, or walking
This migration of pain is a classic hallmark of appendicitis and an important diagnostic clue.
Associated Symptoms
As inflammation continues, further symptoms may appear:
- Low-grade fever: reflecting a localized infection
- Changes in bowel habits: constipation or, occasionally, diarrhea
- Abdominal bloating or distension: often from reduced bowel activity
These findings vary with the stage of disease and the individual.
Physical Signs
On examination, several findings support the diagnosis:
- Localized tenderness at McBurney’s point
- Rebound tenderness, indicating irritation of the peritoneum
- Guarding, an involuntary protective tightening of the abdominal muscles
Certain specific signs may also be elicited:
- Rovsing’s sign: pain in the right lower quadrant when the left lower quadrant is pressed
- Psoas sign: pain when the right hip is extended, suggesting irritation of the psoas muscle
- Obturator sign: pain when the flexed hip is rotated inward, indicating involvement of a pelvic appendix
These signs help pinpoint the inflammation and strengthen diagnostic confidence.
Atypical Presentations
Not everyone shows the classic pattern, and atypical presentations are common in certain groups.
- Children: Symptoms may be less specific and advance quickly. Diagnosis can be difficult, and the risk of perforation is higher.
- Elderly patients: They often have milder or delayed symptoms, which can lead to late diagnosis and more complications.
- Pregnant women: The growing uterus pushes the appendix upward, which can move the pain away from the usual right lower quadrant.
- Retrocecal appendix: When the appendix lies behind the cecum, pain may be less localized and abdominal tenderness less obvious.
Knowing about these variations is essential to avoid missed or delayed diagnosis.
Diagnosis of Appendicitis
Clinical Evaluation
Diagnosis begins with a careful history and physical examination.
- Clinicians focus on the order and progression of symptoms, a key distinguishing feature of appendicitis
- The classic pattern is initial pain around the navel that later settles in the right lower quadrant
- Associated symptoms such as loss of appetite, nausea, and fever add further support
The physical exam plays a central role:
- Identifying localized tenderness, especially at McBurney’s point
- Detecting peritoneal signs such as rebound tenderness and guarding
Recognizing how symptoms evolve over time is often more valuable than any single finding.
Laboratory Tests
Lab studies help support the diagnosis and gauge the degree of inflammation.
- White blood cell count (WBC): Elevated levels (leukocytosis) are common and reflect an inflammatory response.
- C-reactive protein (CRP): A raised level supports the presence of inflammation and may correlate with severity.
- Urinalysis: Done to exclude urinary tract infections or kidney stones, which can mimic appendicitis.
These tests are useful but not specific, and they must be interpreted in clinical context.
Imaging
Imaging is used to confirm the diagnosis, particularly when clinical findings are unclear.
- Ultrasound: Often the first choice in children and pregnant women because it involves no radiation. It can show an enlarged, non-compressible appendix, though results can depend on the operator.
- CT scan: Considered the gold standard in adults, with high sensitivity and specificity. It shows the appendix in detail and can detect complications such as perforation or abscess.
- MRI: An alternative when CT isn’t appropriate, particularly in pregnancy. It offers high diagnostic accuracy without radiation.
Imaging has markedly improved diagnostic accuracy and reduced unnecessary surgeries.
Complications of Appendicitis
Left untreated, appendicitis can progress to serious, potentially life-threatening complications.
- Perforation (ruptured appendix): Occurs when rising pressure and ischemia weaken the appendix wall, letting its contents leak into the abdominal cavity.
- Peritonitis: Inflammation and infection of the peritoneum, causing widespread abdominal pain, rigidity, and systemic illness.
- Abscess formation: A localized pocket of pus that can form around a perforated appendix and often needs drainage.
- Sepsis: A severe body-wide response to infection that can cause organ dysfunction and requires urgent care.
The risk of complications rises sharply with delayed diagnosis.
How Appendicitis Is Treated
Treatment depends on how severe the condition is and whether complications are present.
In most cases, surgical removal of the appendix remains the standard of care.
Surgical Management
Appendectomy is the definitive treatment and is usually performed as soon as the diagnosis is confirmed.
There are two main surgical approaches:
- Laparoscopic appendectomy: Minimally invasive, done through small incisions with a camera and specialized instruments. It is associated with:
- Faster recovery
- Less pain after surgery
- Lower risk of wound complications
- Open appendectomy: Done through a larger incision in the right lower abdomen. It is typically reserved for complicated cases or when laparoscopy isn’t feasible.
Timing matters. Early surgery lowers the risk of perforation and other complications.
Non-Surgical Management
In selected cases of uncomplicated appendicitis, non-surgical treatment may be considered.
- Antibiotics can treat the inflammation and infection without immediate surgery
- Patients must be carefully selected and closely monitored
This approach has limitations, however:
- There is a risk of recurrence, which may require surgery later
- It is unsuitable for complicated cases or suspected perforation
Management of Complicated Appendicitis
When complications such as an abscess or perforation are present, management may differ:
- Abscess drainage: May be done through the skin under imaging guidance to control the infection.
- Delayed surgery (interval appendectomy): In some cases, surgery is postponed until the acute inflammation settles, lowering operative risk.
This staged approach allows the patient to stabilize before definitive treatment.
Postoperative Care and Recovery
Recovery after appendectomy is generally straightforward, particularly in uncomplicated cases.
Still, proper aftercare is essential for good healing, fewer complications, and a safe return to normal activity.
Pain Management
Pain after surgery is usually mild to moderate and can be controlled effectively with:
- Oral pain relievers such as acetaminophen or nonsteroidal anti-inflammatory drugs (NSAIDs)
- Short-term opioids in selected cases, especially after open surgery
Good pain control matters not only for comfort but also for breathing, mobility, and recovery.
Early Mobilization
Getting moving early is strongly encouraged after surgery.
- Patients are usually advised to sit up and walk within the first 24 hours
- Moving early reduces the risk of complications such as blood clots, atelectasis (partial lung collapse), and muscle deconditioning
A gradual return to normal physical activity is recommended, based on how each person recovers.
Diet Progression
Diet is typically advanced in stages:
- Intake may start with clear liquids once nausea settles
- Progression to a regular diet is usually quick in uncomplicated cases
Most patients tolerate normal food within a few days, though a lighter diet may be preferred at first.
Recovery Timelines
Recovery depends on the type of surgery and the severity of the disease:
- Laparoscopic appendectomy: Most people resume normal activities within 1 to 2 weeks.
- Open appendectomy or complicated cases: Recovery may take 2 to 4 weeks or longer, depending on the extent of inflammation and any complications.
Returning to strenuous activity should be guided by clinical recovery and physician advice.
Possible Complications After Surgery
Appendectomy is generally safe, but complications can occur, especially in advanced or perforated cases:
- Wound infection: shown by redness, swelling, or discharge
- Intra-abdominal abscess: especially after perforation
- Postoperative ileus: a temporary slowdown in bowel function
- Adhesions: scar tissue that may cause bowel obstruction later (rare)
Recognizing and managing these complications early is essential for a smooth recovery.
Appendicitis Prevention
There is no guaranteed way to prevent appendicitis, since it often results from a sudden blockage of the appendix.
Some factors may help, however:
- A fiber-rich diet may reduce the risk of fecalith formation by promoting regular bowel movements
- Good overall digestive health may indirectly lower risk
Most importantly, recognizing symptoms early and getting prompt medical evaluation remains the most effective way to prevent complications.
Prognosis
The outlook is generally excellent when appendicitis is diagnosed and treated early.
- Uncomplicated appendicitis: Patients typically recover fully with minimal long-term effects.
- Delayed diagnosis: Raises the risk of perforation, abscess, and peritonitis.
- Mortality: Overall mortality is low, particularly in young, otherwise healthy people, but it rises in complicated appendicitis, especially among elderly patients or those with other health conditions.
Timely treatment remains the single most important factor in outcomes.
When to Seek Medical Attention
Prompt medical evaluation is essential if appendicitis is suspected. Seek care if you have:
- Persistent abdominal pain, especially in the right lower quadrant
- Fever along with abdominal symptoms
- Worsening pain, particularly if it becomes sharp or localized
- Nausea, vomiting, or inability to eat that doesn’t improve
FAQs
1. Where is the appendix located?
The appendix is a small, tube-shaped structure attached to the start of the large intestine (the cecum).
It usually sits in the right lower abdomen, though its exact position can vary slightly from person to person.
2. Which side is the appendix on?
It is on the right side of the body, in the lower right quadrant of the abdomen. That is why appendicitis pain most often occurs there.
And in females? It is in the same general area as in males, the right lower abdomen.
However, nearby reproductive organs can sometimes make diagnosis harder, since symptoms may overlap with gynecological conditions.
3. Where is appendix pain felt?
It usually begins near the belly button (periumbilical area) and then shifts to the right lower abdomen, where it grows more intense and localized.
This shift in pain is a key feature of appendicitis.
4. What are the symptoms of appendicitis?
Common symptoms include:
- Abdominal pain that shifts to the right lower side
- Loss of appetite
- Nausea and vomiting
- Low-grade fever
- Abdominal bloating
Symptoms may worsen over several hours as inflammation progresses.
5. Can the appendix burst?
Yes. If appendicitis isn’t treated promptly, the appendix can burst (perforate).
This usually happens within 24 to 72 hours of the first symptoms and can lead to serious complications such as peritonitis or abscess formation.
Disclaimer
This article is for informational and educational purposes only. We are not medical professionals, and this content does not replace professional medical advice, diagnosis, or treatment.
The goal is to offer accurate, evidence-based information to raise awareness of appendicitis. If you have persistent, severe, or concerning symptoms, seek guidance from a qualified healthcare provider.