12 Early Warning Signs of Frontotemporal Dementia to Watch for
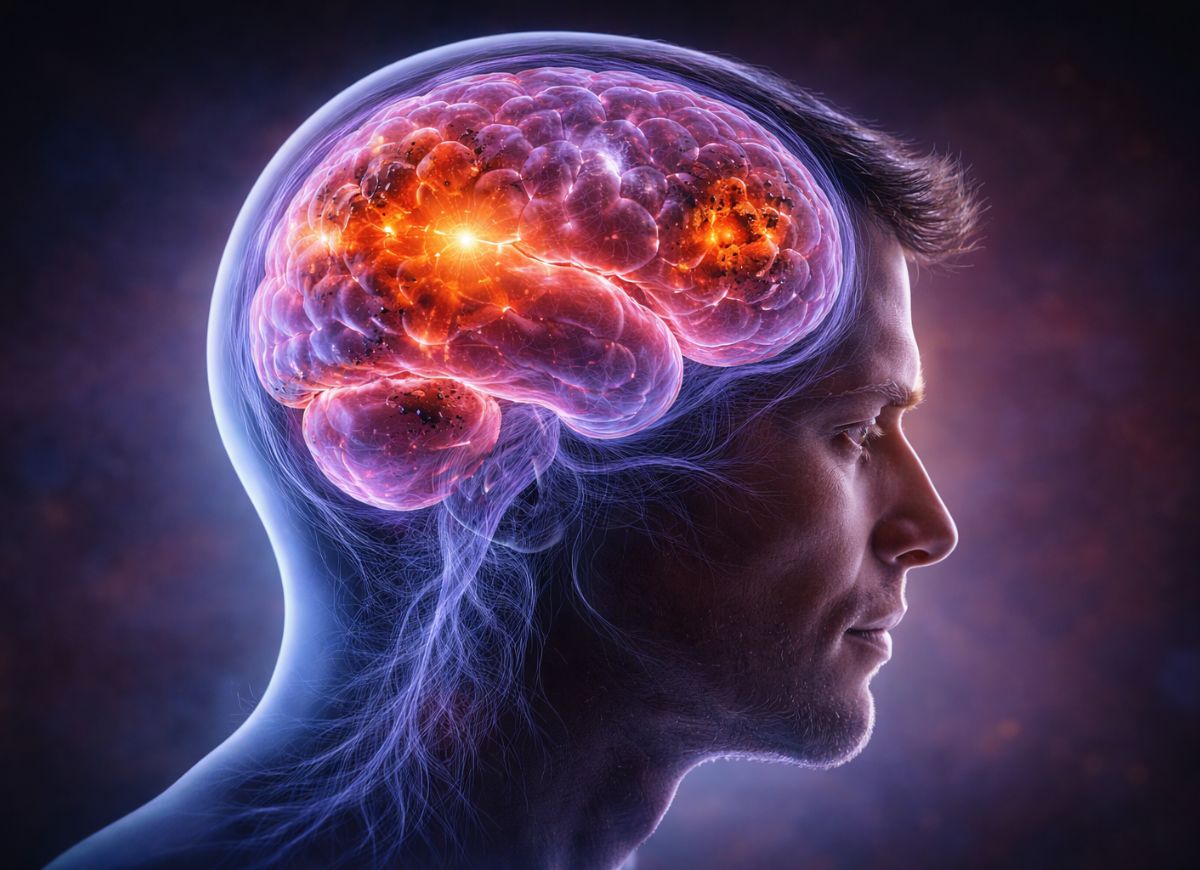
When most people hear “dementia,” they think of Alzheimer’s disease. That makes sense, because Alzheimer’s is the most common form and gets a lot of media attention, with its memory loss and confusion affecting millions. But there is another form that is often overlooked and just as important to recognize: frontotemporal dementia (FTD).
FTD makes up only about 5 to 10% of all dementia cases, but it can deeply affect individuals and their families. It often starts much earlier than Alzheimer’s, typically between ages 40 and 65.
Alzheimer’s mainly affects memory, while FTD mainly targets the frontal and temporal lobes of the brain, which control personality, behavior, and language. As a result, people with FTD may not lose memory at first. Instead, they show dramatic changes in behavior, personality, and social interactions. These early signs are easily mistaken for normal aging or mental health problems, so early detection matters.
In the early stages, FTD is hard to spot because its symptoms look like stress, depression, or simple forgetfulness. Recognizing them early can make a big difference in getting the right treatment and support. Some people show changes in judgment, become socially inappropriate, or act impulsively, while others struggle with language and communication.
In this guide, we go through the 12 early warning signs of frontotemporal dementia. Knowing them helps you seek professional help sooner and improve quality of life for those affected.
What are the Early Warning Signs of Frontotemporal Dementia?
Here are the 12 early signs of frontotemporal dementia:
- A deep loss of empathy
- Socially inappropriate or impulsive behavior
- Growing apathy
- Compulsive actions
- Major changes in eating habits
- A gradual loss of the ability to produce or understand language
- Tremors
- Muscle rigidity
- Poor coordination
- Falls
- Muscle spasms
- Difficulty swallowing or speaking
Together, these form a distinct cluster: dramatic changes in personality and behavior, a steady decline in language and speech, or the start of movement problems.
Primary Changes in Behavior and Personality
The main behavioral and personality changes in FTD are a deep loss of empathy, socially inappropriate or impulsive behavior, growing apathy, compulsive actions, and major changes in eating habits.
These are the hallmarks of the most common form, behavioral variant FTD (bvFTD). They come from the breakdown of the frontal lobes, which control planning, judgment, and social conduct.
- Apathy: one of the most widespread symptoms. The person loses motivation, interest, and emotional response. They may seem lazy or depressed and withdraw from hobbies, work, and social life they once enjoyed. This is not sadness but a dulling of emotion and drive.
- Loss of empathy: the person may become cold and detached and unable to notice or respond to other people’s feelings. They may make insensitive comments, seem indifferent to a loved one’s distress, or miss social cues, which puts heavy strain on relationships.
- Disinhibition: the person loses their social filter. This can lead to offensive or sexually explicit remarks, neglect of personal hygiene, or impulsive acts like reckless spending or shoplifting. Judgment becomes so impaired that they are vulnerable to scams and poor financial decisions.
- Compulsive behavior: this can include rigid routines, hoarding, or repeating the same phrases or movements over and over.
- Changes in eating: a classic sign. Many people develop a strong craving for sweets, overeat compulsively, and may even try to eat things that are not food.
This mix of behavioral and personality decline, while memory and sense of direction often stay intact, is the defining feature of early FTD.
Key Difficulties With Language and Speech
The main language problem in FTD is a gradual loss of the ability to produce or understand language, called Primary Progressive Aphasia (PPA).
Unlike the occasional word-finding trouble most people have, PPA is a steady decline that becomes the central problem in a person’s life. The exact pattern depends on which part of the brain’s language network is hit first, which creates different sub-types.
- Word-finding difficulty (anomia): the person struggles to find the right names for objects, people, or ideas. Speech becomes hesitant, with pauses and vague words like “thing” or “that stuff.”
- Loss of word meaning (semantic variant, svPPA): the person still speaks fluently and grammatically but slowly loses the meaning of words. They may not be able to identify a common object when it is named or explain what it does. For example, they might see a toaster and be unable to recall the word or its use. This loss extends to objects, people, and facts, so speech sounds empty or vague.
- Trouble with speech production and grammar (nonfluent/agrammatic variant, nfvPPA): speech becomes slow, effortful, and laborious. The person struggles to form words and often drops small connecting words like “the,” “is,” and “and,” producing short, telegraph-like sentences. They know what they want to say but have great difficulty getting it out.
Reading and writing are often affected in the same way. In all forms of PPA, language problems are the most prominent feature early on, while memory and reasoning may stay relatively intact.
Early Movement-related Problems in FTD
Early movement problems in FTD include tremors, muscle rigidity, poor coordination, falls, muscle spasms, and difficulty swallowing or speaking.
These are less common as the first sign of FTD but define certain related disorders that overlap with conditions like Parkinson’s disease. When they appear, they show that the damage is reaching brain areas that control movement, in addition to the frontal and temporal lobes. These conditions are Progressive Supranuclear Palsy (PSP) and Corticobasal Syndrome (CBS), both considered part of the FTD spectrum.
Progressive Supranuclear Palsy (PSP): the most prominent early signs are balance and mobility problems. People often have unexplained falls, typically backward, and develop stiffness, especially in the neck and trunk, that gives them a rigid, upright walk. A classic sign is trouble moving the eyes, especially looking down, which makes eating or going down stairs hard. They may also have a mask-like face with little expression, trouble swallowing (dysphagia), and slurred speech (dysarthria).
Corticobasal Syndrome (CBS): movement problems are usually asymmetrical, starting on one side of the body and staying worse there. Symptoms can include stiff limbs, clumsiness, and muscle jerks or spasms (myoclonus). A very specific sign is alien limb phenomenon, where a limb, usually an arm, feels as if it is acting on its own. People may also have apraxia, meaning they cannot carry out purposeful movements such as using a fork or brushing their teeth, even though their muscles are not weak.
Behavioral and thinking symptoms are also part of these disorders, but the early and prominent movement problems help doctors tell them apart within the FTD spectrum.
What is Frontotemporal Dementia?
Frontotemporal Dementia (FTD) is a group of brain disorders caused by the progressive loss of nerve cells in the frontal lobes (behind the forehead) and temporal lobes (behind the ears).
This damage leads to decline in behavior, personality, and language. Unlike Alzheimer’s, FTD usually starts earlier, often between 45 and 65, and memory loss is not typically an early symptom.
The Effect of Frontotemporal Dementia
FTD mainly affects the frontal and temporal lobes, the control centers for our most complex human traits: personality, emotion, behavior, and language. The symptoms a person gets depend on which lobe, and which parts within it, are most affected.
The frontal lobes sit right behind the forehead and handle executive functions: planning, problem-solving, decision-making, judgment, impulse control, and social behavior. They act as the brain’s CEO, shaping personality and helping us handle social situations. When they break down, as in behavioral variant FTD (bvFTD), this control system fails. The result is apathy (loss of motivation), disinhibition (saying or doing inappropriate things), poor judgment, and loss of empathy, because the brain circuits that manage these behaviors are destroyed.
The temporal lobes sit on the sides of the brain, roughly behind the ears. They help process emotions, understand language, and store semantic memory, which is our knowledge of words, concepts, and facts. When the damage mainly hits the temporal lobes, especially the left one in most right-handed people, the result is a language-focused disorder called Primary Progressive Aphasia (PPA).
If the front parts of the temporal lobes are affected, it can lead to Semantic Variant PPA, where the person loses the meaning of words and concepts. They can speak fluently, but their speech becomes empty and they no longer understand what familiar words stand for. This part of the brain works like our internal dictionary and encyclopedia, and in FTD its pages are slowly erased.
Is Frontotemporal Dementia a Hereditary Condition?
In a large share of cases, yes. Genetics plays a much stronger role in FTD than in Alzheimer’s disease.
Most cases are sporadic, meaning there is no known family history, but an estimated 30% to 40% are familial. In these families the disease is passed down, usually in an autosomal dominant pattern. If a parent carries the mutation, each child has a 50% chance of inheriting it and likely developing the disorder. This strong genetic link is one of the features that set FTD apart from other dementias.
Researchers have found several gene mutations behind most familial cases. The three most common are C9orf72, MAPT (microtubule-associated protein tau), and GRN (progranulin).
- C9orf72: the most frequent genetic cause of both FTD and amyotrophic lateral sclerosis (ALS). People with this mutation can develop either or both conditions.
- MAPT: mutations disrupt the normal function of the tau protein, causing it to form abnormal clumps, or tangles, inside neurons, which eventually kills the cells.
- GRN: mutations cause a shortage of progranulin, a protein thought to be involved in cell survival and inflammation, which leads to a different type of protein clump (TDP-43).
Finding these genes was a major breakthrough. It allows genetic testing for people with a strong family history and gives researchers key targets for future drugs. For families with a known mutation, genetic counseling is essential for understanding the risks and making decisions about testing.
Main Types of Frontotemporal Dementia
There are two main types of FTD, classified by the symptoms that appear first: Behavioral Variant Frontotemporal Dementia (bvFTD) and Primary Progressive Aphasia (PPA).
This classification matters because it shows the first and biggest challenges the person will face, which guides diagnosis, management, and family expectations.
Behavioral Variant FTD (bvFTD)
Behavioral Variant FTD is the most common subtype. It is defined by deep, progressive changes in personality, social behavior, and executive function, and it is caused by the breakdown of the frontal lobes, which regulate judgment, empathy, foresight, and impulse control.
In other dementias, memory loss is the first sign. In early bvFTD, memory is often fully intact, which makes diagnosis very hard. The first signs are changes in character that are often mistaken for depression, bipolar disorder, or just poor life choices.
The core features are apathy, disinhibition, and loss of empathy.
- Apathy: a severe lack of motivation and initiative. The person may sit for hours doing nothing, neglect work or household duties, and lose interest in former hobbies and family activities.
- Disinhibition: loss of social filters, leading to behavior that is embarrassing or shocking to family. This includes rude or tactless comments, inappropriate social behavior such as being overly familiar with strangers, and impulsive acts like compulsive gambling, shoplifting, or binge eating.
- Loss of empathy: a devastating symptom. The person becomes emotionally distant and cold and cannot recognize or respond to others’ feelings. They may seem selfish and unconcerned about how their actions affect loved ones.
People with bvFTD also often develop compulsive, repetitive, or ritual-like behaviors, such as hoarding, humming a tune over and over, or following a rigid daily schedule. These deep changes in personality and conduct, without major memory or spatial problems early on, define this subtype.
Primary Progressive Aphasia (PPA)
In PPA, the first and main symptom is a gradual decline in language, while memory, reasoning, and visual perception stay largely intact in the early stages.
“Aphasia” means being unable to understand or form language because of brain damage. In PPA this is not caused by a stroke or head injury but by the slow breakdown of the brain’s language centers, usually in the left temporal and frontal lobes. As the disease advances, other thinking and behavioral symptoms may appear, but language remains the biggest problem for at least the first two years, which is a key diagnostic rule.
PPA has three main sub-variants, each with its own pattern of language loss.
- Nonfluent/Agrammatic Variant (nfvPPA): the problem is speech production. Speech becomes slow, hesitant, and effortful. The person struggles to form words and build correct sentences and often leaves out small connecting words. They know what they want to say but find it physically hard to say it, a condition called apraxia of speech. Understanding single words is usually fine, but complex sentences can be hard.
- Semantic Variant (svPPA): the core problem is loss of word meaning. Speech stays fluent and grammatical but becomes vague and empty because the person has lost the concepts behind words. They may not understand common words spoken to them and can no longer recognize familiar objects, faces, or places. It is a steady erosion of the brain’s store of conceptual knowledge.
- Logopenic Variant (lvPPA): the main feature is trouble retrieving words. Speech is slow with frequent pauses as the person searches for the right word, and they often talk around words they cannot find. lvPPA is grouped under PPA, but its underlying cause is most often Alzheimer’s disease, not the proteins linked to FTD, which makes it distinct in its biology.
Frontotemporal Dementia Diagnosis
Diagnosing FTD requires a thorough clinical evaluation to rule out other conditions, since its symptoms overlap with psychiatric disorders and other dementias like Alzheimer’s.
Getting an accurate diagnosis is a multi-step process. It combines a detailed patient history, neurological exams, cognitive testing, and advanced brain imaging to find the patterns of brain damage typical of FTD. There is no single test that confirms it. Doctors combine several methods to build a full picture and rule out other causes.
- Neurological exam: a specialist checks reflexes, muscle strength, balance, coordination, and sensation to look for signs of nerve damage.
- Neuropsychological testing: a trained psychologist gives detailed tests of problem-solving, memory, language, and executive function, which help show deficits that fit FTD rather than other dementias.
- MRI scan: can reveal shrinkage (atrophy) in the frontal and temporal lobes.
- PET scan: can show reduced activity in those same regions, pointing to areas where nerve cells are not working properly.
- Genetic testing: may be recommended when there is a known family history, to look for mutations such as MAPT, GRN, or C9orf72 linked to inherited forms.
This combined approach gives doctors the best chance of an accurate diagnosis.
Frontotemporal Dementia vs. Alzheimer’s Disease
Both are progressive brain diseases, but they differ greatly in when they start, what the first symptoms are, and which brain regions they affect. This difference is critical for accurate diagnosis and care.
The clearest differences are age at onset and first signs. FTD usually starts earlier, with most diagnoses between ages 45 and 65, while Alzheimer’s is more common after 65. The first symptoms also contrast sharply. Alzheimer’s typically begins with memory loss, especially trouble remembering recent events, because it first affects the hippocampus. FTD first targets the frontal and temporal lobes, causing clear changes in personality, behavior, and language, while memory may stay fairly intact early on.
Support Resources for Families Caring for Someone with FTD
Many support resources exist for families and caregivers dealing with FTD. Caring for someone with the disease brings emotional, physical, and financial strain, largely because of the deep personality and behavior changes involved. Getting specialized support is essential both for the caregiver’s well-being and for the quality of life of the person with FTD.
National advocacy groups are a main source of information and help. The Association for Frontotemporal Degeneration (AFTD) is a leading resource in the United States. It offers educational materials, a helpline for direct support, and links to clinical trials and research. It also helps run local support groups where caregivers can meet others with similar experiences, which reduces isolation and offers practical advice.
Beyond formal groups, online communities and forums offer round-the-clock peer support, letting caregivers in different places share strategies and encouragement. Many hospitals and dementia care centers also run caregiver education programs that teach how to manage difficult behaviors, navigate the healthcare system, and plan for future care. Using these resources gives families knowledge, community, and coping tools to keep going through the caregiving journey.
How to Slow Down the Progression of Frontotemporal Dementia
Right now there is no cure for FTD, and no treatment can slow or stop the underlying disease. The nerve damage that causes FTD is irreversible. That does not mean nothing can be done. The focus of treatment is managing symptoms to improve comfort, keep the person safe, and support quality of life for as long as possible.
The standard of care is a team approach using various therapies and, in some cases, medication. Non-drug approaches are usually the first step.
- Speech therapy: helps people with language-type FTD develop other ways to communicate.
- Occupational therapy: helps adapt the home for safety and simplify daily tasks as executive function declines.
- Physical therapy: helps maintain mobility and balance and lowers the risk of falls.
As for medication, no drugs are specifically approved for FTD, but doctors may prescribe some off-label to manage behavioral symptoms. For example, selective serotonin reuptake inhibitors (SSRIs) may help control compulsive behavior or mood swings, and atypical antipsychotics may be considered for severe agitation or aggression, though they must be used with great caution because of possible side effects in older adults with dementia.
The goal of these treatments is not to change the course of the disease but to manage its effects and support both the person and their caregivers.
FAQs
1. How long can a person live with frontotemporal dementia?
Life expectancy varies, but on average people live 6 to 8 years after symptoms begin. The speed of progression differs from person to person, and factors such as symptom severity, overall health, and access to good medical care all play a role.
Some people live longer if the disease progresses more slowly or if complications are managed well. Because FTD often leads to severe mental and physical decline, early diagnosis and proper care are crucial for improving quality of life.
2. What are the 7 stages of frontal lobe dementia?
The stages can be described in order, but not everyone goes through all of them in the same way. The seven stages typically include:
- Stage 1: subtle personality and behavior changes that are hard to notice, such as minor lapses in judgment or social behavior.
- Stage 2: more emotional outbursts, impulsive behavior, and worse decision-making. The person may struggle to keep up relationships.
- Stage 3: noticeable mental decline, including trouble with complex tasks, language problems, and impaired memory.
- Stage 4: more disinhibition and worsening judgment, with clearer speech difficulties and trouble managing daily tasks.
- Stage 5: severe behavior problems, including agitation and aggression. Communication becomes difficult and the person depends more on caregivers.
- Stage 6: advanced mental and physical decline. The person is often unable to speak or walk and may no longer recognize close family.
- Stage 7: complete loss of movement, speech, and independent mobility. The person is fully dependent on others for everything, including feeding and hygiene.
3. Who is most likely to get frontotemporal dementia?
FTD tends to affect people between ages 40 and 65, which makes it one of the more common dementias in younger adults. Anyone can develop it, but people with a family history are at higher risk, especially if a known genetic mutation runs in the family.
People with a history of neurodegenerative diseases such as Alzheimer’s or Parkinson’s may also have a slightly higher risk. Because symptoms often begin in midlife, the impact on career and personal life can be large, which makes early detection and support essential.
4. Do people with FTD realize they have it?
Many people with FTD do not realize they have it, especially early on. This lack of awareness, called anosognosia, is common in many dementias and is especially noticeable in FTD.
FTD mainly affects the frontal lobes, which control judgment, self-awareness, and decision-making, so people may not fully understand how much their behavior and thinking have changed. Family members and caregivers often notice the changes before the person does, which can make care harder.
5. What is the most aggressive form of dementia?
FTD is often considered the most aggressive form of dementia because of its rapid progression and early onset. Alzheimer’s is more common and usually progresses slowly, while FTD can cause major behavioral and cognitive decline in a fairly short time, sometimes within just a few years.
People with FTD may go through dramatic personality changes, loss of inhibitions, and trouble speaking or understanding language faster than people with Alzheimer’s. This often calls for a higher level of care and support as the disease advances.
6. What’s worse, frontotemporal dementia or Alzheimer’s?
It depends on how you define “worse.” The two diseases affect different parts of the brain and cause different symptoms. Alzheimer’s usually starts with memory loss, while FTD often begins with changes in behavior and personality.
Alzheimer’s tends to progress slowly over many years, while FTD can progress faster, leading to quicker decline in thinking, communication, and behavior. The emotional toll on families can be equally deep in both, as both take away independence and personality. Both diseases are devastating, and which is “worse” depends on each person’s experience and its impact on their life.
7. Can someone with frontotemporal dementia live alone?
Living alone with FTD can be hard, especially as the disease progresses. In the early stages, some people can manage certain activities on their own. As thinking and behavior symptoms worsen, many need help with daily tasks.
Being unable to manage money, cook meals, or keep up hygiene can make it unsafe for people with advanced FTD to live alone. Caregivers need to step in as the disease progresses to provide care and supervision, especially when the person’s judgment and safety are at risk.
8. What does end stage FTD look like?
In the end stage, the person is completely dependent on caregivers for every part of daily life. Communication becomes very limited, and many people can no longer speak or understand others.
There is often a loss of movement skills, including being unable to walk, feed oneself, or make basic movements. The person may become bedridden and may have added problems like difficulty swallowing, which raises the risk of aspiration pneumonia. At this stage, full-time care is needed for every activity, and the condition can lead to declining health and eventually death.
9. What can be mistaken for frontotemporal dementia?
Several conditions can be mistaken for FTD, especially early on when symptoms overlap with mental health disorders. Depression, bipolar disorder, or schizophrenia can cause similar behavior changes like irritability, impulsivity, or social withdrawal.
Alzheimer’s disease can also be confused with FTD, especially when memory loss becomes prominent early on. Doctors need to tell these conditions apart using brain imaging, genetic testing, and thorough assessments to make sure the diagnosis and treatment are correct.
Conclusion
Frontotemporal dementia is a rare but debilitating condition that mainly affects the frontal and temporal lobes of the brain, causing major changes in behavior, personality, and thinking.
Recognizing the early warning signs is crucial for timely action and care planning. FTD progresses quickly in many cases, but understanding the condition and its effect on the person and their loved ones can make it easier to manage.
By seeking medical advice and early treatment, families can help make sure the affected person gets the best care possible. FTD brings unique challenges, but knowing the symptoms, causes, and management options leads to better outcomes and a better quality of life for those living with it.