What Is an Epidural Steroid Injection? A Complete Guide
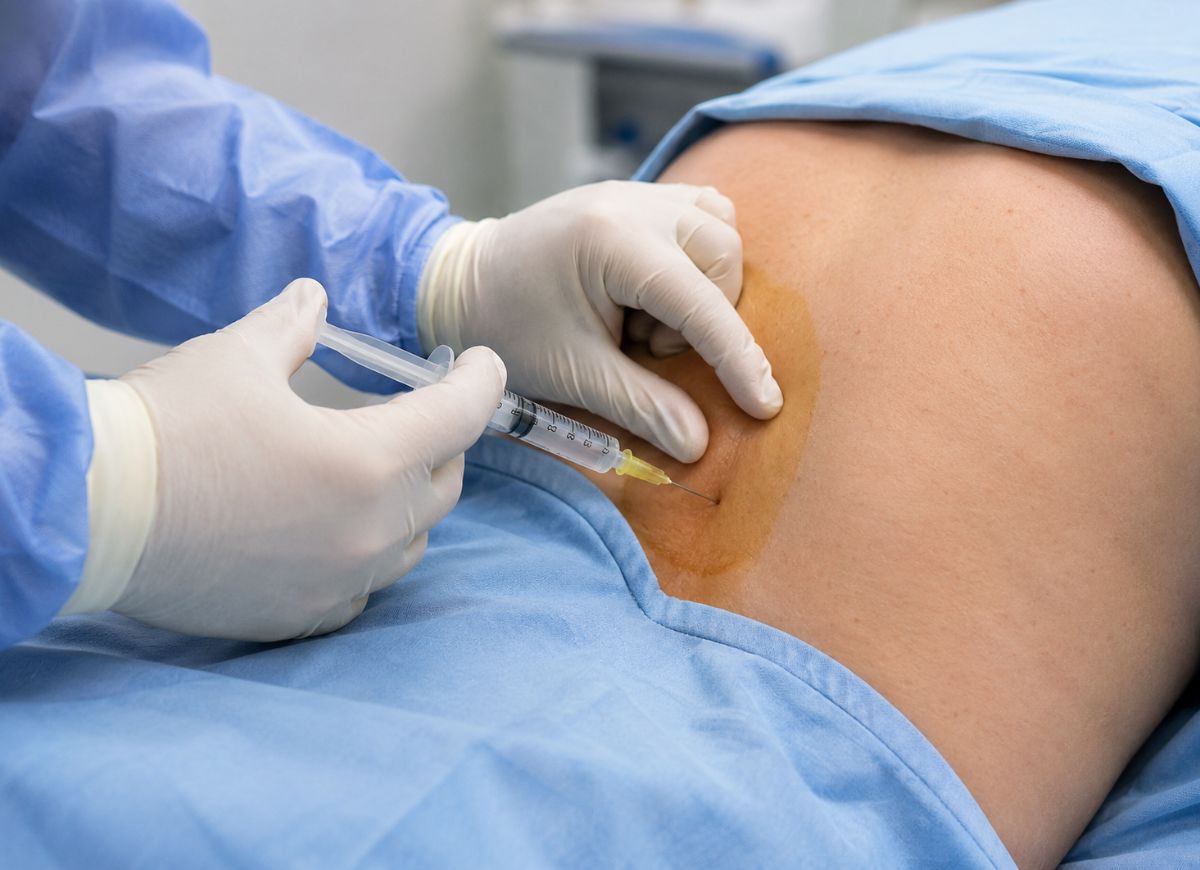
What if a single injection could ease persistent back pain and help you move more freely again? An epidural steroid injection is a widely used treatment designed to relieve pain caused by inflammation or irritation around the spinal nerves. For people dealing with herniated discs, sciatica, spinal stenosis, or other types of nerve-related back pain, this procedure can offer meaningful, if temporary, relief and improved daily function.
The spine houses a network of nerves that carry signals throughout the body. When these nerves get compressed or inflamed, the result can be pain, numbness, tingling, or weakness that spreads from the back into the arms or legs. An epidural steroid injection delivers a corticosteroid, often paired with a local anesthetic, into the epidural space around these nerves to calm inflammation and quiet pain signals.
Unlike surgery, this procedure is minimally invasive and typically done on an outpatient basis. Most patients go home the same day and may notice improvement within days, though outcomes vary depending on the underlying cause and its severity.
Epidural steroid injections aren’t a cure-all for every kind of back or nerve pain. How well they work depends on the condition being treated, a person’s overall health, and their individual response. Doctors typically use these injections as one piece of a larger pain management plan that might also include physical therapy, exercise, medication, or lifestyle adjustments.
Understanding how the procedure works, why it’s recommended, and what recovery looks like can help patients make more informed choices about their care. This guide covers what an epidural steroid injection is, how it works, the conditions it treats, its benefits and risks, what the procedure involves, and what to expect during recovery.
Effectiveness of Epidural Steroid Injections
Epidural steroid injections are a legitimate, commonly used non-surgical option for chronic pain stemming from spinal nerve inflammation, capable of offering temporary but meaningful relief that helps set the stage for recovery. Their real value lies in breaking the cycle of inflammation and pain, opening up a window where patients can engage in rehabilitative work like physical therapy that tackles the underlying mechanical problems.
To appreciate what these injections can and can’t do, it helps to understand the mechanism behind them and set realistic expectations. Some patients do get lasting relief, but ESIs tend to work best as a short-to-medium-term tool within a broader pain management strategy, rather than a standalone, permanent fix.
An Epidural Steroid Injection
An epidural steroid injection (ESI) is a minimally invasive procedure that delivers a potent anti-inflammatory medication, usually a corticosteroid, directly into the epidural space of the spine. This is the fat-filled area surrounding the dural sac, the protective membrane that holds the spinal cord, nerve roots, and cerebrospinal fluid.
The goal of an ESI isn’t to fix a structural problem like a herniated disc or spinal stenosis outright. It’s to aggressively treat the inflammation those conditions cause. That inflammation is what irritates and compresses spinal nerves, leading to the debilitating pain, numbness, tingling, or weakness that can radiate into the arms or legs, a condition called radiculopathy.
The mechanism actually works on two fronts, since most injections combine a corticosteroid with a local anesthetic. The corticosteroid itself (dexamethasone or triamcinolone, for example) is a powerful anti-inflammatory agent. Once injected into the epidural space, it spreads through the area and reduces the production of inflammatory chemicals and cellular responses right at the irritated nerve root. This lowers swelling and pressure on the nerve, easing pain. The effect isn’t instant; it typically takes two to seven days for the anti-inflammatory action to peak and produce noticeable relief.
Many physicians also mix in a fast-acting local anesthetic, such as lidocaine or bupivacaine. This provides immediate, though temporary, pain relief that can last several hours. That quick effect serves an important diagnostic purpose too. If a patient’s typical pain drops significantly right after the injection, it helps confirm that the targeted nerve root and spinal level really are the main source of their symptoms, information that’s valuable for planning future treatment, including surgery if it ever becomes necessary.
By delivering medication directly to the source of inflammation, ESIs skip the systemic circulation that oral medications have to travel through. That allows a higher concentration of the drug to reach exactly where it’s needed, while lowering the chance of side effects elsewhere in the body.
How Successful Injections Are for Providing Short-term vs. Long-term Relief
Epidural steroid injections are considerably more reliable for short-term pain relief, lasting anywhere from a few weeks to several months, than they are for delivering sustained, long-term results, which tend to be far less predictable.
How well an injection works depends heavily on the underlying diagnosis, how accurately it’s placed, and how committed the patient is to a rehabilitation program during the window of relief. That’s why physicians tend to treat ESIs as a functional tool rather than a final cure.
Short-term outcomes are generally encouraging. Studies and clinical experience consistently show that a majority of patients, often cited at 50% to 70% or higher for conditions like lumbar disc herniation with radiculopathy, get significant pain reduction. This relief usually kicks in within a few days as the steroid takes effect and can last for months.
That reduced-pain window is really the whole point of the procedure. It gives patients a chance to break free from the pain-immobility cycle and participate more fully in physical therapy, stretching, and strengthening exercises that address the core mechanical issues behind their condition. In this sense, the ESI acts as a bridge toward more durable, activity-based treatment.
Long-term relief from a single injection, on the other hand, is less common. The corticosteroid’s anti-inflammatory effect naturally fades over time, and if the underlying structural issue (severe spinal stenosis or a large disc herniation, say) is still there, inflammation and pain tend to come back. Eventually, the body metabolizes and clears the steroid from the epidural space entirely. So patients who lean on the injection alone, without pairing it with other therapies, often see their symptoms return.
Some patients manage their condition longer-term through a series of injections, usually capped at three or four a year to limit steroid-related side effects. For a smaller group, particularly those with acute inflammation that resolves during the treatment window, one or two injections may be all it takes for lasting relief as the body heals on its own. For chronic conditions, though, ESIs are best thought of as part of ongoing pain management rather than a permanent solution.
Procedure for Epidural Steroid Injections
Patients getting an epidural steroid injection can expect a well-defined, minimally invasive outpatient process: pre-procedure prep, a core injection guided by imaging that takes 15 to 30 minutes, and a short recovery and monitoring period afterward. The whole process is built around safety, accuracy, and patient comfort, from the first consultation through the follow-up check on pain relief.
Walking through the process ahead of time helps ease patient anxiety and ensures they know what to expect at each stage. The procedure is typically performed by a specialist, such as an anesthesiologist, physiatrist, or radiologist with training in interventional pain management, who guides the patient through the steps and gives clear before-and-after instructions.
Conditions Epidural Steroid Injections Primarily Treat
Epidural steroid injections primarily treat inflammatory spinal conditions that cause radicular pain, pain that radiates from the back or neck along the path of a compressed or irritated spinal nerve.
The treatment works best when inflammation is a major factor in a patient’s symptoms. It’s generally not very effective for pain that’s purely mechanical or localized to the back or neck without radiating elsewhere. The goal is to calm the inflamed nerve root and reduce pain, numbness, tingling, and weakness in the limbs.
Lumbar Disc Herniation is one of the most common reasons for an ESI. It happens when the soft, gel-like center of a spinal disc pushes through a tear in its tougher outer layer. This herniated material can press directly on a nearby nerve root, and since it’s also highly inflammatory, it can cause severe chemical irritation of the nerve, leading to sciatica or lumbar radiculopathy, with pain shooting down the leg.
As people age, spinal discs can lose hydration, shrink, and develop tears, a condition called Degenerative Disc Disease. Many people with DDD have no symptoms at all, but in some cases, the breakdown of the disc releases inflammatory proteins that irritate nearby nerves, and bone spurs may form and add to nerve compression. An ESI can help manage the inflammatory flare-ups that come with this chronic condition.
Lumbar Spinal Stenosis involves narrowing of the spinal canal, the passage through which the spinal cord and nerve roots travel. This narrowing can come from overgrown facet joints, thickened ligaments, or bulging discs, and it puts pressure on the nerves, often causing neurogenic claudication: pain, cramping, or weakness in the legs that worsens with standing or walking and eases with sitting or bending forward. ESIs can reduce inflammation in that constricted space, offering temporary relief.
Sciatica isn’t a diagnosis itself but a symptom describing pain that radiates along the sciatic nerve, which runs from the lower back through the hips and buttocks and down each leg. It’s most commonly caused by a herniated disc or spinal stenosis compressing a nerve root. ESIs are a frontline non-surgical treatment for acute sciatica driven by inflammation.
How the Epidural Steroid Injection Procedure Is Performed
The procedure is carried out by a trained physician using fluoroscopy, live, real-time X-ray, to ensure the needle is placed precisely and safely into the epidural space before injecting contrast dye and the steroid medication.
Imaging guidance is the standard of care here, since it dramatically improves accuracy and lowers the risk of complications compared to blind injections. The whole process is methodical and usually wraps up in 15 to 30 minutes.
1. Patient Preparation and Positioning: The patient is brought into a procedure room and positioned on a specialized table, usually face down for lumbar injections or on their side. The medical team connects monitors to track vital signs like heart rate, blood pressure, and oxygen levels throughout. The skin over the injection site is cleaned thoroughly with an antiseptic solution to prevent infection.
2. Local Anesthesia: The physician numbs the skin and deeper tissue at the injection site with a local anesthetic like lidocaine. Patients might feel a brief sting or burning sensation as it’s administered, but it quickly numbs the area before the larger epidural needle goes in.
3. Needle Placement with Fluoroscopy: Using continuous imaging, the physician guides a thin, hollow needle through the numbed tissue toward the epidural space. Depending on the patient’s anatomy and where the inflammation is located, the physician may use an interlaminar, transforaminal, or caudal approach. The live X-ray lets them track the needle’s path relative to the spine’s bones, ensuring correct placement.
4. Confirmation with Contrast Dye: Once the needle tip appears correctly positioned, a small amount of contrast dye is injected. This dye shows up on the fluoroscope, creating an “epidurogram” that confirms two things: that the needle sits in the epidural space rather than a blood vessel or the dural sac, and that the medication will spread to reach the targeted nerve roots.
5. Injection of Medication: Once placement is confirmed, the physician slowly injects the medication mixture, typically the corticosteroid along with a local anesthetic. Some patients feel a sense of pressure, but it shouldn’t be painful.
6. Post-Procedure: The needle is removed and a small sterile bandage covers the entry site. The patient then moves to a recovery area for roughly 20 to 40 minutes of observation, to check for any immediate reaction, before being discharged home with a driver.
Benefits vs. Risks of Epidural Steroid Injections
The main benefit of epidural steroid injections is targeted, non-surgical pain relief, but that has to be weighed against potential risks and side effects. The best candidates are patients with confirmed inflammatory radicular pain who haven’t responded to more conservative treatment. A thorough evaluation by a qualified physician is essential to figure out whether the benefits outweigh the risks for any given patient.
That assessment involves comparing ESIs to alternatives like surgery, understanding who’s most likely to respond well, and being fully aware of the range of possible side effects, from common and mild to rare but serious.
Primary Benefits of Choosing ESIs Over Surgery
Compared to spinal surgery, the main advantages of ESIs are that they’re minimally invasive and outpatient, come with a dramatically faster recovery, and let patients sidestep the significant risks tied to major surgery. For many people with debilitating radicular pain, ESIs act as a powerful intermediate step that can delay, or even eliminate, the need for surgery altogether.
The entire procedure is done with a needle, not a scalpel. That means no incisions, no stitches, and minimal disruption to surrounding muscle and tissue, a sharp contrast to surgical procedures like laminectomies or fusions, which require significant tissue dissection and come with more post-operative pain and a higher risk of scarring.
Most patients are advised to take it easy for the rest of the day after an ESI but can typically resume normal activities within 24 to 48 hours. Surgical recovery, by comparison, is a much longer process, often taking weeks to months and requiring extensive rehab along with significant time off work and other activities.
Surgery, especially spinal surgery, carries real risks: complications from general anesthesia, significant blood loss, post-operative infection, blood clots, and potential nerve damage during the operation. Fusion surgeries add the risk of hardware failure, failed bone fusion, and adjacent segment disease, where the levels above and below the fusion break down faster. ESIs avoid all of these major risks entirely.
An ESI can also work as a diagnostic tool. A transforaminal ESI, which targets a specific nerve root, can help pinpoint exactly where a patient’s pain is coming from. If the injection provides significant temporary relief, it confirms that nerve is the source, which is extremely useful information for surgical planning down the line, should surgery become necessary.
Taken together, these benefits make ESIs a compelling option that prioritizes patient safety and quality of life, whether as a bridge to recovery or a standalone treatment for acute inflammation.
Common Side Effects and Rare Complications
The common side effects of epidural steroid injections tend to be mild, self-limiting, and temporary, things like soreness at the injection site or facial flushing, while rare complications are more serious and can include infection, significant bleeding, or nerve damage.
ESIs are considered very safe when performed by an experienced physician using imaging guidance, but patients should still be aware of the full range of possible outcomes.
Mild, common side effects are generally not dangerous and clear up on their own within hours to a few days. Soreness or aching at the injection site is the most common, and it’s easily managed with ice and over-the-counter pain relievers. Some patients experience a brief “steroid flare,” where their usual radicular pain temporarily worsens for a day or two before the anti-inflammatory effect kicks in. “Steroid flush” causes temporary redness and warmth in the face and chest, a harmless systemic effect of the corticosteroid.
Steroids can also cause mild systemic effects like temporary anxiety, trouble sleeping, or slight fluid retention for a few days. Patients with diabetes should monitor their blood sugar closely for a few days afterward, since corticosteroids can temporarily raise it.
Rare but serious complications are statistically uncommon but require immediate medical attention. Though extremely rare thanks to sterile technique, infection can occasionally reach the epidural space or the membranes around the spinal cord, a medical emergency marked by fever, severe headache, neck stiffness, and worsening back pain.
Bleeding into the epidural space can form a hematoma that compresses the spinal cord or nerve roots, potentially causing paralysis; the risk is highest for patients with bleeding disorders or those on blood thinners. Direct nerve injury from the needle is possible too, though fluoroscopy makes it exceedingly rare, and it could cause persistent pain, numbness, or weakness.
If the needle accidentally passes through the dura mater, it can cause a cerebrospinal fluid leak, leading to a severe positional headache that’s much worse sitting or standing and eases when lying down. Most dural punctures heal on their own, but some need a procedure called an epidural blood patch to seal the leak. A severe allergic reaction to the corticosteroid, anesthetic, or contrast dye is also possible, though very rare.
Exploring Deeper Aspects and Alternatives to Epidural Injections
Getting a fuller picture of epidural steroid injections means looking at the specific types available, how they stack up against other treatments, and how they fit into a broader, multi-faceted pain management plan that may include complementary therapies.
Digging into these details helps patients make more informed decisions, moving beyond the basic concept of the injection to understand the nuances of how it’s applied and where it fits alongside other approaches.
Different Types of Epidural Steroid Injections
Epidural steroid injections are categorized mainly by the path the needle takes to reach the epidural space. The choice depends on the patient’s anatomy, where the inflammation is located, and the physician’s expertise.
The three main types are Interlaminar, Transforaminal, and Caudal, each approaching the problem from a different angle. The interlaminar approach, often considered the most traditional, involves inserting the needle from the back of the spine between two adjacent vertebral plates to deliver medication into the posterior epidural space.
The transforaminal ESI, sometimes called a nerve block, instead directs the needle from the side of the spine into the opening where the nerve root exits the spinal canal. This allows for more targeted delivery of the steroid directly onto the irritated nerve.
The caudal approach inserts the needle through a small bony opening at the very bottom of the spine to reach the epidural space, often used for widespread pain in the lower back and legs.
Interlaminar ESIs work well for diffuse or central pain, such as spinal stenosis or disc herniations affecting a broader area, since the medication spreads more widely through the epidural space. Transforaminal ESIs are highly specific and ideal for radiculopathy caused by a herniated disc compressing a particular nerve root, and their precision often provides useful diagnostic information. Caudal ESIs are often preferred for patients who’ve had previous lumbar spine surgery, since scar tissue can make the other two approaches difficult, and they work well for pain coming from multiple lower lumbar nerve roots, such as in degenerative disc disease or sciatica affecting both legs.
Epidural Injections and Other Non-surgical Pain Treatments
Epidural steroid injections occupy a distinct place in non-surgical pain management, offering a targeted, interventional approach that differs significantly from more conservative methods like physical therapy, oral medications, or chiropractic care. While an ESI delivers a potent anti-inflammatory directly to the source of nerve irritation, these other treatments work through different mechanisms entirely.
Oral anti-inflammatory medications, like NSAIDs, offer systemic relief by reducing inflammation throughout the body, but they lack the precision of an injection, may cause gastrointestinal side effects, and are often less potent. Physical therapy is an active treatment focused on rehabilitation, addressing the underlying biomechanical issues through exercises that strengthen core muscles, improve flexibility, and correct posture, aiming for long-term stability rather than immediate relief. Chiropractic care involves manual spinal manipulation to improve alignment and mobility, which can ease nerve pressure and reduce pain.
Each treatment has its own ideal use case, and they’re often most effective combined as part of a comprehensive plan. ESIs directly combat chemical inflammation around nerve roots. Physical therapy corrects mechanical and muscular imbalances. Oral medications reduce systemic inflammation. Chiropractic adjustments aim to restore proper joint mechanics through spinal manipulation.
An ESI typically provides rapid, short-to-medium-term relief, creating a window of opportunity for other therapies to work more effectively. Physical therapy and chiropractic care focus on gradual, long-term functional improvement and prevention, requiring active participation over weeks or months. ESIs suit patients with specific inflammatory conditions like severe sciatica or spinal stenosis who haven’t responded to conservative care, while physical therapy is fundamental for nearly all musculoskeletal pain, chiropractic care is often sought for mechanical back pain, and oral medications serve as a first-line option for acute or mild-to-moderate inflammatory pain.
The Difference Between Epidural Steroid Injections and Facet Joint Injections
While both epidural steroid injections and facet joint injections are common interventional procedures for spine-related pain, they target entirely different structures and address different sources of discomfort.
An epidural steroid injection targets the epidural space, the region surrounding the spinal cord and nerve roots as they exit the spine. The goal is to reduce inflammation of those nerve roots, which often causes radicular pain, sharp, shooting pain that travels from the back or neck into a limb, as in sciatica or cervical radiculopathy. In essence, an ESI treats pain coming from irritated nerves.
A facet joint injection, by contrast, delivers medication, typically a corticosteroid and local anesthetic, directly into the facet joints, the small, stabilizing joints on the back of the spine between each vertebra that guide movement. When these joints become arthritic or inflamed, they cause axial pain, a dull, aching pain typically localized to the neck or lower back that may sometimes refer to the shoulders or buttocks, but doesn’t follow a specific nerve path.
Alternative or Complementary Therapies to Consider Alongside ESIs
A successful chronic pain management strategy rarely relies on just one treatment. Epidural steroid injections tend to work best as part of a holistic, multidisciplinary plan that includes complementary therapies.
These approaches work together: the injection reduces severe pain to a manageable level, opening a window for the patient to engage more effectively in rehabilitative work that addresses the root causes of pain. Physical therapy is arguably the most critical partner to an ESI. While the injection reduces inflammation, physical therapy corrects the underlying mechanical issues, strengthens core and back muscles for better spinal support, improves flexibility, and teaches proper body mechanics to prevent future injury.
Acupuncture, an ancient practice involving thin needles inserted at specific points on the body, is another valuable complementary therapy, thought to stimulate the nervous system, release pain-relieving endorphins, and improve energy flow, helping manage chronic pain and muscle tension. Massage therapy can also help by releasing tight muscles, improving circulation, and reducing stress, all of which feed into the cycle of chronic pain.
Beyond physical treatments, therapies addressing the psychological side of chronic pain matter too, and can significantly boost the effects of interventional procedures. Cognitive-Behavioral Therapy helps patients identify and change negative thought patterns tied to chronic pain, offering coping strategies and ways to reframe the pain experience that improve daily function and quality of life.
Mindfulness-based stress reduction teaches patients to focus on the present moment without judgment, which can help detach from the overwhelming sensation of pain, ease anxiety, and build a greater sense of control. Yoga and Tai Chi combine physical postures, breathing techniques, and meditation, improving flexibility, balance, and strength while promoting relaxation and reducing the stress that often makes chronic pain worse.
FAQs
1. What are the side effects of an epidural steroid injection?
Most people tolerate epidural steroid injections well, but side effects can occur. Common short-term effects may include soreness at the injection site, a temporary increase in pain, flushing, headache, dizziness, or changes in blood sugar. Less common risks include infection, bleeding, nerve irritation, or a reaction to the medication. Your doctor will weigh your health history and risk factors before recommending the procedure.
2. What is the recovery time for an epidural injection?
Recovery is usually quick compared to surgical treatments. Many people go home the same day and resume light activities shortly after. Some notice pain relief within a few days, while others take longer. Recovery time can vary depending on the condition being treated and how the individual responds.
3. What should I avoid after an epidural steroid injection?
Patients are often advised to avoid strenuous exercise, heavy lifting, and activities that strain the back for a short period afterward. It’s also important to follow your provider’s specific instructions regarding activity levels, medications, and monitoring for unusual symptoms.
4. What is the success rate of epidural steroid injections?
Effectiveness varies depending on the cause of pain, injection location, and individual health factors. Many people get meaningful temporary relief, especially those with nerve-related pain from conditions like herniated discs or spinal inflammation. Results differ from person to person, and the injection is usually considered part of a broader pain management plan.
5. Why do people say no to epidurals?
People may decline epidural injections due to concerns about side effects, discomfort, cost, fear of needles, or personal preference. Some prefer other approaches like physical therapy, medication, or lifestyle changes. The decision depends on each person’s situation, pain level, and conversation with their healthcare provider.
6. Is bed rest required after an epidural?
Bed rest generally isn’t required. Most people are encouraged to move gently and return gradually to normal activities based on their doctor’s advice. Avoiding excessive strain right after the procedure can help support recovery.
Conclusion
An epidural steroid injection can be a helpful option for people dealing with certain types of back, neck, or nerve-related pain. By delivering medication near irritated spinal nerves, the procedure can reduce inflammation and provide relief that makes it easier to participate in daily activities and rehabilitation.
While the treatment offers real benefits, it isn’t right for everyone and doesn’t permanently fix every cause of pain. Understanding the potential benefits, risks, recovery process, and expected results can help patients make informed decisions.
Working closely with a healthcare provider is important for figuring out whether an epidural steroid injection fits your condition and goals. With the right treatment plan, many people find they can better manage pain and improve their quality of life.