10 Key Warning Signs of Thrombotic Thrombocytopenic Purpura
Have you ever wondered which symptoms could point to a rare blood disorder before it becomes more serious? Thrombotic Thrombocytopenic Purpura (TTP) is an uncommon condition that causes tiny blood clots to form in small blood vessels throughout the body. Because TTP can progress quickly and become life-threatening, recognizing possible warning signs and getting urgent medical care is important.
TTP affects an estimated 3 to 11 people per million each year, making it a rare disorder. It can occur at any age but is diagnosed more often in adults and is more common in women. The condition can develop suddenly, so understanding its symptoms can help people recognize when something may be wrong.
TTP is usually linked to a severe deficiency of an enzyme called ADAMTS13. This enzyme normally helps regulate von Willebrand factor (vWF), a protein involved in blood clotting. When ADAMTS13 activity becomes severely reduced, unusually large vWF molecules can cause platelets to form tiny clots inside small blood vessels. These blockages can interfere with blood flow to organs such as the brain, kidneys, and heart.
The symptoms of TTP can vary and may initially resemble other medical conditions. Possible warning signs include unusual bruising, small red or purple spots on the skin, severe tiredness, weakness, headaches, confusion, fever, and symptoms caused by low platelets or reduced blood flow.
Because TTP can worsen rapidly, suspected cases require urgent medical evaluation. Modern treatments have greatly improved outcomes, particularly when the condition is identified and treated quickly.
In this article, we’ll cover the 10 key warning signs of Thrombotic Thrombocytopenic Purpura, why they can occur, and when urgent medical attention may be necessary.
What is Thrombotic Thrombocytopenic Purpura (TTP)?
Thrombotic Thrombocytopenic Purpura is a rare and potentially life-threatening blood disorder in which very small blood clots develop throughout the body’s small blood vessels.
The condition is most often caused by a severe shortage of functional ADAMTS13, an enzyme that normally keeps a blood-clotting protein called von Willebrand factor under control. When this regulation is lost, platelets can collect abnormally and form microscopic clots.
These clots can reduce blood flow to important organs, including the brain, heart, and kidneys. At the same time, the excessive use of platelets can cause a very low platelet count, increasing the risk of bleeding.
The name describes several important features of the condition. “Thrombotic” refers to blood clots, “thrombocytopenic” means a low platelet count, and “purpura” describes purple spots or bruises caused by bleeding beneath the skin.
TTP is considered a medical emergency because organ damage can develop rapidly without appropriate treatment.
What Happens In the Body During a TTP Episode?
During a TTP episode, two major problems occur at the same time: tiny blood clots form throughout small blood vessels, and the platelet supply drops significantly.
The process begins when ADAMTS13 cannot properly regulate von Willebrand factor. Without enough working ADAMTS13, unusually large vWF molecules remain in the bloodstream and can capture platelets.
These platelets then collect into tiny clots called microthrombi. The clots can block small blood vessels and reduce blood flow to different parts of the body.
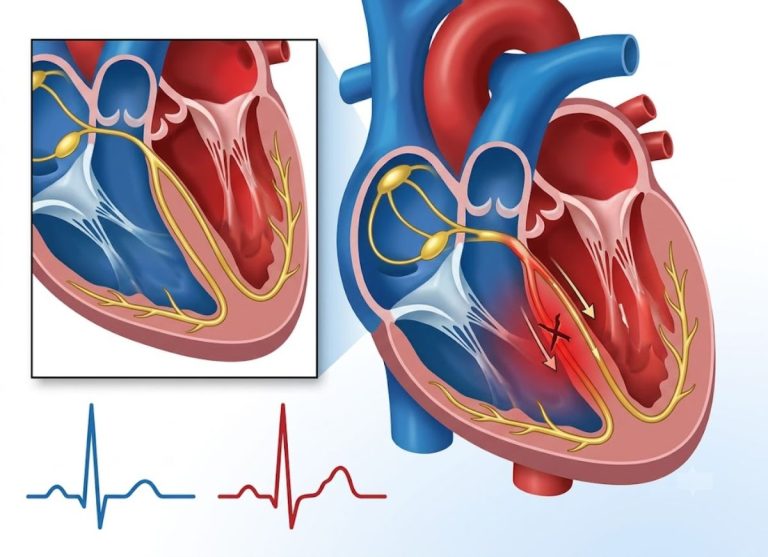
The brain, heart, and kidneys are particularly vulnerable. Reduced blood flow to the brain can cause headaches, confusion, neurological changes, or stroke-like symptoms. Heart involvement may cause chest discomfort or other signs of reduced blood supply, while kidney involvement can interfere with normal kidney function.
As platelets are continually consumed to form these small clots, the platelet count can fall significantly. This thrombocytopenia makes it harder for the body to stop bleeding, which can result in purpura, petechiae, and other bleeding symptoms.
TTP can also damage red blood cells. As they travel through blood vessels containing microclots, the cells can become fragmented. This process is called hemolysis and can lead to hemolytic anemia, causing symptoms such as severe fatigue, weakness, shortness of breath, and sometimes jaundice.
Is Thrombotic Thrombocytopenic Purpura a Life-threatening Condition?
Yes. TTP can become life-threatening without prompt diagnosis and treatment.
The small clots associated with TTP can interfere with blood flow to vital organs and may cause serious complications involving the brain, heart, or kidneys. Neurological symptoms can sometimes progress quickly, and severe organ damage may occur if treatment is delayed.
Historically, untreated TTP had a very high mortality rate. Modern treatments, particularly plasma exchange and immune-targeting therapies, have substantially improved survival.
Because the condition can deteriorate rapidly, suspected TTP requires immediate medical assessment. Doctors may begin treatment based on the clinical picture while specialized laboratory testing is still being completed.
10 Key Symptoms of Thrombotic Thrombocytopenic Purpura
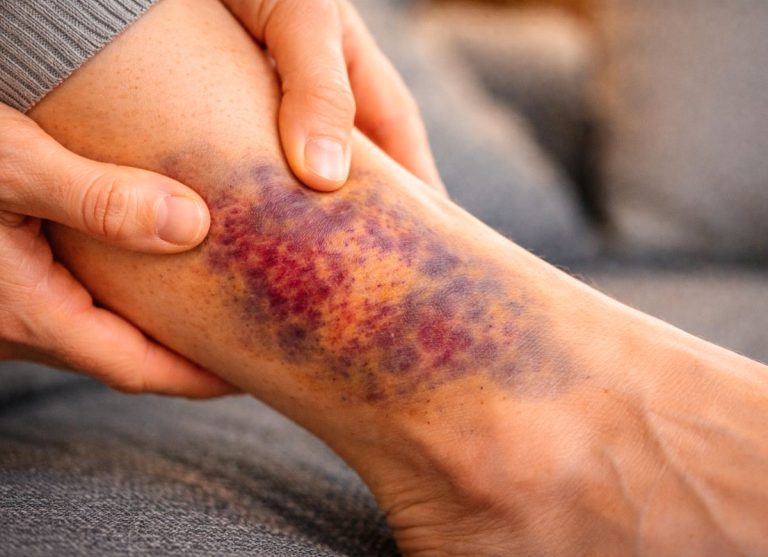
Purpura
Purpura are purple or reddish-purple spots that can appear on the skin or mucous membranes.
Unlike ordinary bruises caused by an injury, purpura associated with low platelet levels may develop without an obvious cause. They result from small amounts of blood leaking beneath the skin.
These spots are generally larger than petechiae and usually do not turn white when pressed.
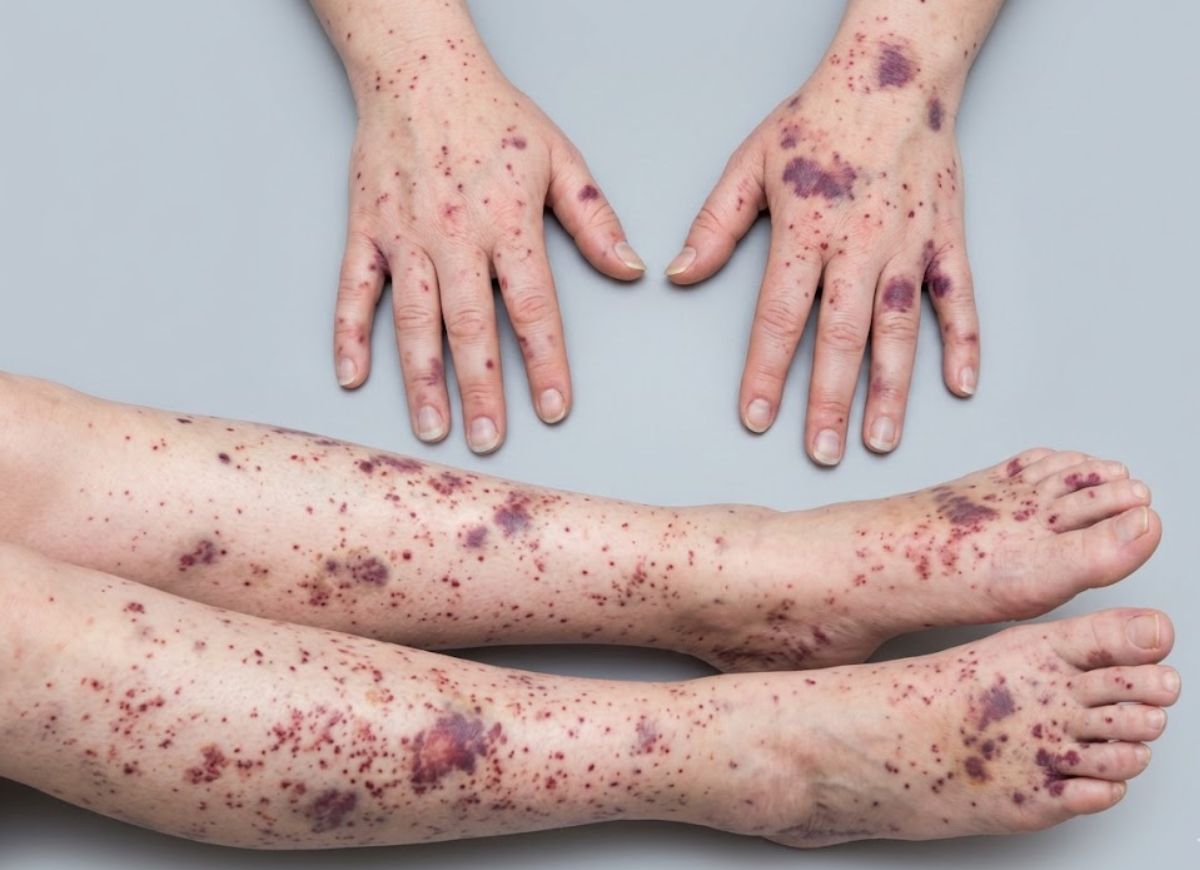
Petechiae
Petechiae are tiny red, purple, or reddish-brown spots caused by small amounts of bleeding beneath the skin.
They may appear in groups and are often noticed on the legs or other areas of the body. Because they can resemble a rash, they may initially be difficult to recognize as bleeding-related spots.
Petechiae typically do not blanch when pressure is applied. A widespread appearance can be a sign of a significantly reduced platelet count.
Unexplained Bleeding
A very low platelet count can make it harder for the body to stop bleeding.
Possible signs include frequent or prolonged nosebleeds, bleeding from the gums, blood in the urine, or blood in the stool. Some people may also experience unusually heavy or prolonged menstrual bleeding.
Bleeding that occurs without an obvious injury or continues longer than expected should be medically evaluated.
Headaches/Dizziness
Headaches can occur during a TTP episode, particularly when the condition affects blood flow to the brain.
Dizziness or lightheadedness may also occur. These symptoms can have several possible causes, including anemia and changes in blood circulation.
A sudden, severe, or unusual headache, especially when accompanied by other neurological symptoms, requires urgent medical attention.
Confusion/Memory Changes
TTP can affect the brain and cause changes in mental function.
A person may experience difficulty concentrating, confusion, disorientation, unusual behavior, or problems with memory. In more serious cases, neurological function can deteriorate significantly.
These symptoms can occur when microclots interfere with blood flow within the brain.
Stroke-like Symptoms
Small blood clots can temporarily or seriously interfere with blood flow to parts of the brain, producing symptoms that resemble a stroke.
Possible signs include sudden weakness or numbness on one side of the body, difficulty speaking or understanding speech, changes in vision, problems with balance, or difficulty coordinating movements.
Seizures and severe changes in consciousness can also occur in serious cases. Any sudden stroke-like symptom should be treated as a medical emergency.
Extreme Fatigue/Weakness
Severe fatigue and weakness are common effects of the anemia associated with TTP.
When red blood cells are destroyed faster than the body can replace them, less oxygen is delivered to tissues. This can result in intense tiredness, weakness, and reduced ability to perform normal activities.
The fatigue may feel much more severe than ordinary tiredness and may not improve adequately with rest.
Shortness of Breath (Dyspnea)
Anemia reduces the amount of oxygen that the blood can carry throughout the body.
As a result, a person may feel short of breath, particularly during physical activity. In more severe cases, breathlessness may occur even with minimal activity.
The heart may also beat faster to compensate for the reduced oxygen delivery, which can cause a rapid heartbeat or noticeable palpitations.
Jaundice or Pale Skin
Changes in skin color can occur because of the destruction of red blood cells.
Anemia may make the skin, nail beds, or inner eyelids appear unusually pale. At the same time, the breakdown of red blood cells produces bilirubin. If bilirubin levels rise, the skin and whites of the eyes may develop a yellowish color known as jaundice.
Fever
Fever can occur during a TTP episode and is traditionally included among the classic features of the condition.
However, fever can have many causes, including infections, so it should not be considered specific to TTP. When fever occurs alongside a low platelet count, anemia, neurological symptoms, or other concerning signs, doctors may investigate TTP and other serious conditions.
TTP can also affect the kidneys because the kidneys contain many small blood vessels. Microclots can interfere with kidney circulation and reduce kidney function.
Possible signs include reduced urine output, blood in the urine, or swelling caused by fluid retention. Blood tests may show increased creatinine and other markers of impaired kidney function.
Although severe kidney injury is more commonly associated with hemolytic uremic syndrome (HUS), kidney involvement can also occur in TTP.
What Causes the Thrombotic Thrombocytopenic Purpura?
TTP develops because the body has severely reduced ADAMTS13 activity.
ADAMTS13 is responsible for controlling the size of von Willebrand factor, a protein that helps platelets form clots when blood vessels are injured.
TTP can develop in two main ways. In acquired TTP, the immune system produces antibodies that interfere with ADAMTS13. In congenital TTP, much less commonly, inherited genetic changes affect the body’s ability to produce functional ADAMTS13.
When ADAMTS13 activity becomes severely deficient, unusually large vWF molecules accumulate and encourage platelets to form tiny clots throughout small blood vessels.
These microclots can reduce blood flow, consume platelets, and damage red blood cells. Together, these processes produce the major symptoms associated with TTP.
The Function of the ADAMTS13 Enzyme
ADAMTS13 helps maintain normal blood clotting by breaking large forms of von Willebrand factor into smaller pieces.
Von Willebrand factor is an important protein involved in the early stages of clot formation. When a blood vessel is injured, vWF helps platelets attach to the damaged area and create an initial platelet plug.
However, very large vWF molecules can cause excessive platelet attachment if they are not properly regulated.
ADAMTS13 normally controls these unusually large vWF molecules by cutting them into smaller forms. This helps prevent inappropriate platelet clumping within small blood vessels.
A Lack of ADAMTS13
When there is not enough functional ADAMTS13, large vWF molecules remain active in the bloodstream.
These molecules can bind large numbers of platelets, resulting in the formation of numerous small blood clots in the body’s microcirculation.
The resulting microthrombi can restrict blood flow and reduce oxygen delivery to organs. This can contribute to neurological symptoms, kidney problems, and heart-related complications.
Because platelets are continually consumed to form these clots, the platelet count falls. This explains why people with TTP may develop purpura, petechiae, nosebleeds, or other bleeding symptoms.
At the same time, red blood cells can become damaged as they pass through vessels containing microclots. This leads to microangiopathic hemolytic anemia, which contributes to fatigue, weakness, and shortness of breath.
The breakdown of red blood cells can also increase bilirubin levels and contribute to jaundice.
Thrombotic Thrombocytopenic Purpura Diagnosis
Diagnosing TTP requires urgent medical evaluation and a combination of clinical findings and laboratory tests.
A complete blood count (CBC) can reveal thrombocytopenia and anemia. Doctors may also perform a peripheral blood smear to look for schistocytes, which are fragmented red blood cells created when cells are damaged while passing through abnormal small blood vessels.
One of the most important tests is an ADAMTS13 activity test. Very low ADAMTS13 activity, particularly activity below 10%, strongly supports a diagnosis of TTP when the clinical picture is consistent with the condition.
Doctors may also order additional blood and urine tests to assess kidney function, check for signs of red blood cell destruction, evaluate possible heart involvement, and rule out other disorders that can resemble TTP.
Because TTP can progress quickly, doctors may begin treatment when the condition is strongly suspected rather than waiting for every test result.
Standard Treatments for Thrombotic Thrombocytopenic Purpura
Treatment for acquired TTP needs to begin quickly because the condition can cause serious organ damage.
Plasma exchange, also known as plasmapheresis or PEX, is a key treatment. During plasma exchange, a machine separates the patient’s plasma from the blood cells. The plasma is replaced with donor plasma containing functional ADAMTS13.
This process helps remove harmful antibodies while replacing the missing enzyme.
Doctors also commonly use medicines that suppress the immune response. Corticosteroids may be used to reduce immune system activity and limit the production of antibodies that interfere with ADAMTS13.
Other treatments may be considered depending on the individual case. Rituximab can target B cells involved in producing harmful antibodies. Caplacizumab works by interfering with the interaction between von Willebrand factor and platelets, helping reduce the formation of new microclots.
Treatment decisions are made by medical specialists based on the severity of the condition and the individual patient’s needs.
TTP vs. HUS
TTP and Hemolytic Uremic Syndrome (HUS) are both thrombotic microangiopathies and can cause low platelets, destruction of red blood cells, and organ problems.
However, their underlying causes are different.
TTP is most commonly associated with severe ADAMTS13 deficiency. In contrast, the most common form of HUS, particularly in children, is often associated with Shiga toxin-producing bacterial infections, including certain strains of E. coli.
The organs affected can also differ. Neurological problems are particularly important in TTP, while kidney injury is often more prominent in HUS.
Because the treatments for these conditions are different, doctors use laboratory testing, clinical findings, and medical history to help distinguish between them.
Long-term Prognosis for Patients after a TTP Diagnosis
The outlook for people with TTP has improved considerably with modern diagnosis and treatment. Prompt plasma exchange and other therapies have changed TTP from a frequently fatal condition into one that many patients survive.
However, recovering from an acute episode does not always mean the condition can be forgotten. Some people experience a recurrence, known as a relapse, so continued medical monitoring may be recommended.
Follow-up care may include regular assessments of ADAMTS13 activity and monitoring for symptoms that could suggest another episode. In some cases, preventive treatment may be considered when ADAMTS13 levels fall.
Some TTP survivors may also experience longer-term effects, including fatigue, difficulties with concentration or memory, mood changes, or other health concerns. Ongoing follow-up can help identify and manage these issues.
FAQs
1. What is the triad of TTP?
The classic features of TTP include thrombocytopenia, hemolytic anemia, and neurological symptoms. Fever and kidney problems may also occur. However, not every person has all of these features, so doctors rely heavily on laboratory testing and the overall clinical picture.
2. What is the cause of Thrombotic Thrombocytopenic Purpura?
TTP is usually caused by severely reduced ADAMTS13 activity. Acquired TTP occurs when the immune system produces antibodies that interfere with the enzyme. Congenital TTP is much rarer and results from inherited changes affecting ADAMTS13.
3. Does TTP go away?
Many people recover from an acute TTP episode with appropriate treatment. However, the condition can sometimes return, so medical follow-up is important after recovery.
4. Is TTP for life?
TTP does not necessarily remain active throughout a person’s life. Some people have one episode, while others experience relapses. Regular monitoring can help doctors identify signs of recurrence.
5. What is the first symptom seen in thrombocytopenia?
Low platelet counts can cause easy or unexplained bruising, petechiae, nosebleeds, bleeding gums, or bleeding that takes longer than usual to stop. Some people may have no symptoms when the platelet count is only mildly reduced.
6. Can vitamin B12 deficiency cause thrombocytopenia?
Severe vitamin B12 deficiency can sometimes cause a low platelet count because it interferes with normal blood cell production. However, thrombocytopenia has many possible causes, so medical testing is needed to determine the reason.
7. What not to eat with TTP?
There is no specific food that causes TTP or a universal diet that treats it. A balanced diet can support general health, while alcohol, supplements, or medications that may increase bleeding risk should be discussed with a healthcare professional, particularly when platelet levels are low.
Conclusion
Thrombotic Thrombocytopenic Purpura is a rare but potentially life-threatening blood disorder that requires rapid medical attention. Recognizing possible warning signs, including unexplained bruising, petechiae, unusual bleeding, severe fatigue, headaches, confusion, and stroke-like symptoms, can help people seek care sooner.
TTP is commonly associated with severe ADAMTS13 deficiency, which allows abnormal platelet-rich clots to form in small blood vessels. These clots can reduce blood flow to important organs and contribute to low platelet counts and red blood cell destruction.
Although TTP can be serious, modern treatments have significantly improved outcomes. Prompt diagnosis, appropriate treatment, and ongoing follow-up can help reduce complications and identify possible relapses.
If someone develops sudden neurological symptoms, unusual bleeding, widespread bruising, or other concerning symptoms associated with TTP, urgent medical evaluation is important.