7 Common Symptoms of Left Ventricular Hypertrophy to Know
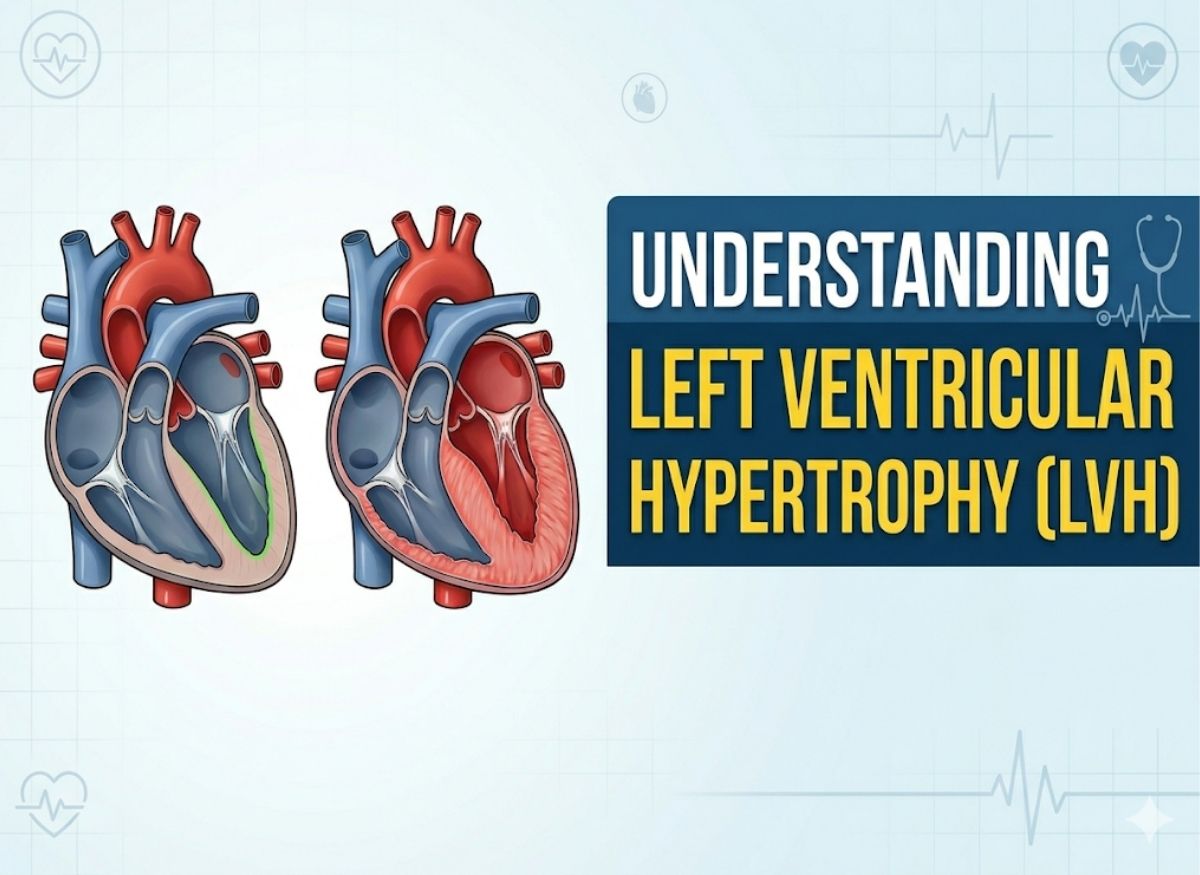
Left ventricular hypertrophy (LVH) is a condition where the muscular wall of the heart’s left ventricle becomes thickened. This thickening tends to develop gradually as the heart works harder to pump blood, often due to conditions like high blood pressure or heart valve problems. Left ventricular hypertrophy may not cause any noticeable symptoms early on, but over time it can affect how efficiently the heart works and raise the risk of serious cardiovascular complications.
Recognizing the symptoms of left ventricular hypertrophy matters for catching and treating it early. Many people brush off subtle signs like fatigue or shortness of breath without realizing they could be tied to heart health. In this article, we’ll walk through the key warning signs, explain how the condition affects the heart, and help you understand when it’s time to see a doctor.
What Is Left Ventricular Hypertrophy?
The left ventricular hypertrophy meaning centers on a significant structural change to the heart’s most important chamber. To define ventricular hypertrophy, you need to look at the left ventricle, the high-pressure chamber responsible for pushing oxygenated blood through the entire body. Ventricular hypertrophy refers to a process where the heart muscle, or myocardium, increases in mass and wall thickness in response to ongoing pressure or volume overload.
Using the LVH medical abbreviation, doctors identify this not as a disease in itself, but as a dangerous adaptation. While a weightlifter’s bicep grows stronger through use, the thickening of left ventricle tissue creates a stiff, oxygen-hungry muscle that eventually compromises the heart’s ability to relax and pump effectively.
The Structural Remodeling of the Heart Muscle
As the workload placed on the heart increases, individual heart muscle cells undergo changes that lead to mild LV hypertrophy. This early thickening is often “concentric,” meaning the muscle grows inward, narrowing the internal space of the ventricle. While this lets the heart generate more force, it also changes the underlying cause behind left ventricular hypertrophy by introducing fibrosis, the buildup of stiff, scar-like tissue between muscle cells.
This stiffness prevents the heart from expanding properly during its filling phase. This is known as diastolic dysfunction, meaning that even if the heart squeezes well, it can’t “reload” with enough blood, causing a backup of pressure that often results in left atrial enlargement markers on an ECG, where the left atrium becomes strained and stretched.
Diagnostic Markers and Severity Levels
Clinical identification of this condition often starts with an ECG assessment for LVH. On an electrocardiogram, the thickened muscle generates higher electrical voltages, which a cardiologist identifies as LVH by voltage criteria. These electrical signals offer a window into the heart’s physical condition, often showing a “strain pattern” that suggests the muscle is struggling. After a suspicious ECG, a doctor typically orders an echocardiogram (a heart ultrasound) to confirm the diagnosis.
This imaging allows for precise classification, such as mild LVH on echo, moderate left ventricular hypertrophy, or severe cases. The echocardiogram also helps distinguish between mild concentric left ventricular hypertrophy, where the walls are thick but the chamber is small, and eccentric left ventricular hypertrophy, where the chamber has stretched and enlarged, often seen in athletes or people with valve regurgitation.
The Long-Term Risks of an Enlarged Left Ventricle
Signs of an enlarged left ventricle on an ECG serve as a warning sign for future cardiovascular problems. Because the thickened muscle needs more oxygen than the coronary arteries can easily supply, patients with moderate left ventricular hypertrophy face a much higher risk of chest pain and heart attack, even without clogged arteries.
The disorganized muscle structure also disrupts the heart’s natural electrical pathways, making it prone to arrhythmias ranging from atrial fibrillation to more dangerous ventricular rhythm disturbances. In the medical community, left ventricular hypertrophy is closely linked to a heightened risk of sudden cardiac death, since the heart becomes both electrically unstable and mechanically less efficient.
Understanding Borderline and Mild Cases
It’s common for patients to receive a report noting borderline LVH or mild LV hypertrophy. While “mild” sounds reassuring, in the context of the heart it means the destructive remodeling process has already begun. In some cases, a patient may show signs of both left and right ventricular hypertrophy, suggesting the underlying pressure issues have affected the whole heart, often due to combined lung and systemic blood pressure problems.
At any stage, the goal of treatment is to identify the underlying causes of left ventricular hypertrophy and intervene aggressively, typically through blood pressure management, to prevent progression from an ECG finding to a full heart failure diagnosis.
7 Warning Signs of Left Ventricular Hypertrophy
Left ventricular hypertrophy often develops during a “silent” period, when the heart’s compensatory mechanisms hide the underlying structural changes. Because the thickening of left ventricle tissue is an adaptive response to stress, the heart initially succeeds at maintaining circulation despite higher resistance. However, the appearance of LVH symptoms marks a critical shift from “compensated” to “decompensated” heart function. When the muscle becomes too thick to get enough oxygen or too stiff to fill with blood, a powerful pump starts to become a failing one.
The Clinical Signature of Diastolic Dysfunction
The most common LVH symptoms, shortness of breath and fatigue, come from the heart’s inability to relax properly. In a healthy heart, the left ventricle expands like a soft balloon to take in blood. In moderate left ventricular hypertrophy, the muscle behaves more like a stiff hose. This lack of flexibility means blood waiting in the left atrium struggles to enter the ventricle, and instead backs up into the lungs.
This creates pulmonary congestion, which explains why a patient might feel fine while sitting but suddenly feel breathless during a walk. This congestion often comes along with left atrial enlargement markers on an ECG, since the left atrium has to work harder to push blood into the stiff ventricle.
The Oxygen Strain of a Thickened Wall
Chest pain, or angina, is a notable warning sign that the thickened left ventricle has outgrown its own oxygen supply. The coronary arteries sit on the outside of the heart and branch inward. In a heart with mild LV hypertrophy, blood can still reach all the muscle layers. But as the condition advances to moderate left ventricular hypertrophy, the muscle wall becomes so thick that pressure inside the chamber squeezes the small internal blood vessels shut.
This creates “demand ischemia,” where the heart muscle is literally starved of oxygen during exertion. This is a leading reason patients feel chest pressure or tightness when climbing stairs.
Electrical Instability and Palpitations
The structural changes involved in ventricular hypertrophy also include interstitial fibrosis, tiny areas of scarring between muscle fibers. These patches of scar tissue act as “electrical roadblocks,” forcing the heart’s natural timing signals to take long, erratic detours. This is why an ECG often shows a “strain pattern” in these cases, and why patients experience heart palpitations.
These fluttering sensations are often the first sign of atrial fibrillation or more serious ventricular arrhythmias. When these irregular rhythms happen, the heart’s output drops instantly, leading to the dizziness or fainting that characterizes more advanced cases.
Fluid Retention and Declining Exercise Tolerance
As the heart’s efficiency continues to decline, the body’s other systems start to feel the impact. Swelling in the legs and ankles, known as edema, happens because the heart can no longer effectively pull blood back up from the lower body, causing fluid to leak into surrounding tissue. This often comes with a noticeable drop in exercise tolerance.
Someone who once walked miles without trouble may find that even a short flight of stairs leaves them exhausted. This decline reflects the heart reaching its functional limit. At this stage, the heart’s adaptive reserves are running out, and the risk of progressing to full congestive heart failure becomes real.
Primary Causes and Risk Factors for Left Ventricular Hypertrophy
Left ventricular hypertrophy is fundamentally rooted in how the heart responds to resistance. When the left ventricle is forced to push blood against a constant obstacle, whether that’s a high-pressure arterial system or a narrowed valve, it undergoes a structural transformation. This explains why thickening of left ventricle tissue is the most common response to chronic cardiovascular stress. Identifying the specific underlying cause is the only way to reverse or slow this potentially dangerous remodeling.
Hypertension: The Chronic Workload
High blood pressure is the leading cause of left ventricular hypertrophy, responsible for the vast majority of cases. In someone with hypertension, the heart must overcome increased “afterload,” the pressure the ventricle needs to generate to open the aortic valve and push out blood. This constant strain acts like non-stop resistance training. The resulting mild concentric left ventricular hypertrophy involves the heart muscle growing inward to strengthen its walls. Over time, this thick-walled chamber becomes stiff and loses its ability to relax, which often shows up on an ECG as a strain pattern.
Mechanical Obstruction: Aortic Valve Stenosis
While hypertension is a systemic pressure problem, aortic valve stenosis is a localized mechanical blockage. The aortic valve serves as the exit door for the left ventricle, and when it becomes calcified and narrowed, the ventricle has to generate enormous pressure to squeeze blood through a tiny opening. This extreme pressure overload leads to some of the most dramatic cases of moderate left ventricular hypertrophy and severe wall thickening. On an ultrasound, this may appear as mild LVH in its early stages but can quickly progress to a point where the muscle becomes so thick it starves itself of oxygen, even with clear coronary arteries.
Genetic Causes: Hypertrophic Cardiomyopathy (HCM)
In some people, thickening of the left ventricle happens without any external pressure at all. Hypertrophic cardiomyopathy is a genetic condition where heart muscle cells are disorganized and prone to spontaneous thickening. This cause isn’t tied to lifestyle but to DNA. Unlike the symmetrical thickening seen with hypertension, HCM often causes “asymmetric” growth, where the septum, the wall between heart chambers, becomes disproportionately large. This can block blood flow out of the heart and is a leading cause of sudden cardiac arrest in young people, making detection through ECG or echo critical for life-saving treatment.
Physiological vs. Pathological: The Athlete’s Heart
It’s important to distinguish between a “sick” heart and a “strong” heart. Elite athletes often develop mild LV hypertrophy, sometimes called “athlete’s heart.” While this can meet LVH voltage criteria on an ECG, it’s actually a healthy adaptation. In athletes, the heart typically undergoes “eccentric” remodeling, where chamber size increases along with a modest rise in wall thickness. Unlike mild concentric left ventricular hypertrophy, the athlete’s heart stays flexible and efficient. Doctors use echo readings to confirm there’s no stiffness or left atrial enlargement, which would instead point to a pathological condition.
Determining the Underlying Cause
What left ventricular hypertrophy means for a given patient depends entirely on which of these factors is driving it. Whether the cause is high-pressure “afterload,” a mechanical valve blockage, or a genetic condition, the heart muscle is under strain. Understanding whether the growth is mild concentric left ventricular hypertrophy (pressure-based) or eccentric left ventricular hypertrophy (volume-based) helps doctors tailor treatment, such as using ACE inhibitors to lower blood pressure or performing surgery to replace a faulty valve.
When Should You See a Doctor About Possible Signs of Left Ventricular Hypertrophy?
The shift from having no symptoms to needing clinical intervention is a pivotal moment in managing left ventricular hypertrophy. Because this condition involves a progressive structural decline, waiting for “obvious” illness can be risky. The goal is to catch it while it’s still mild, before the muscle develops the irreversible fibrosis seen in moderate cases. Seeking medical evaluation isn’t just about relieving symptoms, it’s about preventing the condition from progressing into permanent heart failure.
Identifying the Emergency Warning Signs
While many LVH symptoms develop slowly, there are three specific situations where thickening of the left ventricle creates an immediate, life-threatening emergency. If any of these happen, skip a standard appointment and seek emergency care right away:
- Crushing Chest Pain: Since the underlying condition involves a muscle that’s already oxygen-hungry, any sudden blockage can trigger a rapid heart attack. Intense pressure that spreads to the jaw or left arm is a sign the thickened muscle is experiencing acute oxygen deprivation.
- Fainting (Syncope): Losing consciousness is a major warning sign of electrical instability. Disorganized muscle fibers in LVH can trigger sudden ventricular tachycardia. If the heart beats too fast or irregularly, blood flow to the brain can stop instantly.
- Acute Pulmonary Edema: A sudden, frightening inability to breathe while at rest suggests the stiff left ventricle has completely backed up, forcing fluid into the air sacs of the lungs.
Preparing for a Diagnostic Evaluation
When you see a specialist to investigate a possible enlarged left ventricle or suspected LVH, the quality of the information you provide matters a lot. A cardiologist uses your input to determine whether the thickening stems from mild concentric left ventricular hypertrophy related to lifestyle, or a more complex cause like genetics.
Tracking Your Symptoms
Instead of vague descriptions, try to provide specific, functional details. Note whether your shortness of breath happens after one flight of stairs or three. Distinguish between a “racing” heart and a “skipped beat” sensation. This helps your doctor determine whether they’re looking at signs of heart failure or an arrhythmia like atrial fibrillation, which often shows up alongside left atrial enlargement markers.
Medication and History
Your doctor needs to know your baseline blood pressure and any medications you’re currently taking, since some drugs can mask or worsen left ventricular thickening. Because hypertrophic cardiomyopathy is highly hereditary, knowing whether a relative passed away suddenly or had “an enlarged heart” at a young age can shift the diagnostic process toward genetic testing.
The Clinical Path: From ECG to Echo
During your visit, the doctor will likely perform an ECG screening for LVH. If the electrical signals show high voltage, they’ll move to an echocardiogram to assess the heart’s structure directly. This ultrasound gives the clearest picture, measuring exact wall thickness to determine whether you have borderline LVH, mild LV hypertrophy, or a more advanced stage. It also checks diastolic filling speed to see how stiff the muscle has become.
How Is LVH Diagnosed and Managed Long-Term?
The diagnostic journey for left ventricular hypertrophy starts with identifying the electrical and structural changes that occur when the heart’s main pump is under strain. To properly define ventricular hypertrophy in a clinical setting, doctors need objective data on muscle mass and wall thickness, not just symptoms. Once an ECG or ultrasound confirms the condition, the focus shifts to long-term management aimed at preventing serious cardiac failure.
Diagnostic Tools: From Screening to Precision
LVH is often first suspected during a routine ECG screening. An electrocardiogram measures the heart’s electrical “voltage,” and as the muscle thickens, it generates more electrical power, showing up as large spikes on the tracing. However, because signs of an enlarged left ventricle can sometimes be a false positive in thin or athletic individuals, doctors rely on echo readings for confirmation.
The echocardiogram allows a cardiologist to calculate the “Left Ventricular Mass Index,” the definitive measure used to categorize the condition as mild, moderate, or severe. For complex cases, especially distinguishing between mild concentric left ventricular hypertrophy and genetic hypertrophic cardiomyopathy, a Cardiac MRI is the most precise tool. It can detect “Late Gadolinium Enhancement,” a marker of the microscopic scarring that makes the heart stiff and prone to failure.
Long-Term Management: Addressing the Root Cause
Treating left ventricular hypertrophy isn’t about “curing” the muscle directly, but about removing the stress that caused it to thicken in the first place. In many cases, aggressive management can lead to regression, where the heart muscle actually thins back toward a healthier state.
- Blood Pressure Control: This is the cornerstone of managing left ventricular hypertrophy. Medications like ACE inhibitors, ARBs, and calcium channel blockers are prioritized because they not only lower pressure but also interfere with the hormonal signals that tell heart cells to grow larger.
- Valve Treatment: If aortic stenosis is the underlying cause, the long-term solution is often a surgical or transcatheter valve replacement (TAVR) to remove the mechanical blockage.
- Lifestyle Changes: Weight loss and reducing sodium intake are essential. Excess weight adds to the volume the heart has to pump, while salt increases the pressure it has to work against. Addressing both provides real relief for left ventricular hypertrophy strain.
Preventing Silent Progression to Failure
The danger of ignoring a borderline or mild LVH diagnosis is the eventual progression toward heart failure. As the muscle stiffens, the heart becomes less efficient, leading to left atrial enlargement, a sign the atrium is stretching under pressure. This stretching is a major trigger for atrial fibrillation, which can lead to life-altering strokes.
By addressing the causes of left ventricular hypertrophy early, patients can avoid the shift from a thick, powerful pump to a dilated, weakened one. Long-term management involves regular check-ups using echo monitoring to confirm muscle thickness is either stable or decreasing. This proactive approach is the best way to protect the heart against the risks of sudden cardiac death and chronic congestive failure.
The Difference Between Physiological (Athlete’s Heart) and Pathological LVH
The core question of what left ventricular hypertrophy means depends on whether the heart’s growth is a healthy adaptation or a defensive, scarring response. While both scenarios may trigger LVH voltage criteria on an initial screening, the underlying cellular structure tells two very different stories. Physiological LVH, or “athlete’s heart,” is a performance upgrade, while pathological LVH represents an ongoing structural failure.
Structural Symmetry and Chamber Volume
In an athlete, remodeling is typically “eccentric.” This means that as heart walls thicken to handle the blood volume needed for intense exercise, the internal chamber also expands. This balanced growth keeps the heart large and efficient.
Pathological growth, often called mild concentric left ventricular hypertrophy, involves walls growing inward instead. This reduces chamber size, leaving less room for blood to fill before each beat. On an ECG showing an enlarged left ventricle, both types may look similar, but an ultrasound reveals that the athlete’s heart has a healthy, large cavity, while the hypertensive heart is cramped and thick.
The Critical Role of Diastolic Function
The most important clinical marker separating these two conditions is “diastolic function,” or the heart’s ability to relax. In pathological LVH, the muscle is infiltrated with fibrous scar tissue, making it stiff and inflexible. This stiffness leads to LVH symptoms like shortness of breath and fatigue, since the heart can’t draw in enough blood from the lungs. In an athlete’s heart, the muscle stays highly elastic. Even with a diagnosis of mild LV hypertrophy, an athlete’s heart shows superior relaxation speeds on an echo test. This elasticity is what lets an elite runner’s heart fill rapidly even at very high heart rates.
Reversibility and Long-Term Risk
The underlying cause also shapes the long-term outlook. Physiological LVH is entirely benign. If an athlete stops training for several months, the heart muscle typically shrinks back to its original size without lasting damage. Pathological LVH, on the other hand, is often irreversible once significant fibrosis has occurred. Treating the underlying causes, like lowering blood pressure, can cause some regression, but the risk of arrhythmias, left atrial enlargement, and heart failure remains much higher than in the general population.
Diagnostic Differentiation
Because treatment for a “thick heart” varies so much between a professional athlete and a patient with chronic hypertension, doctors rely on specialized testing to tell them apart. If an ECG shows high voltage in a young person, a doctor will look for a “strain pattern,” a specific dip in the ST-segment of the heart wave. A strain pattern almost always points to a pathological cause. An echo report showing a dilated left atrium is also a strong indicator of a pathological state, suggesting the atrium is struggling to push blood into a stiff, diseased ventricle.
Can Lifestyle Changes Help Manage or Reverse Left Ventricular Hypertrophy?
A diagnosis of left ventricular hypertrophy isn’t a fixed sentence of decline, it’s a dynamic condition that can respond remarkably well to treatment. While the definition of ventricular hypertrophy involves structural thickening, the heart has a degree of flexibility that allows for “reverse remodeling.” By aggressively addressing the underlying causes through lifestyle changes, it’s possible to shift from moderate left ventricular hypertrophy back toward mild hypertrophy, or even a normal heart mass.
The Direct Impact of Sodium and Weight on Heart Mass
The most powerful lifestyle lever for reversing LVH is reducing systemic pressure. Sodium intake is a major driver of fluid retention, which increases the volume of blood the heart must move. Following a diet like DASH and strictly limiting salt reduces the “afterload,” or the resistance the heart has to work against.
Weight loss is equally important, since every extra pound of tissue requires miles of new capillaries, all of which the left ventricle has to supply with blood. Losing weight reduces this “volume overload,” a key contributor to left ventricular hypertrophy. Clinical studies have shown that significant weight loss alone can lead to regression of an enlarged left ventricle, since the heart no longer needs such a massive muscle wall to support a smaller body.
Aerobic Exercise: Training the Heart for Efficiency
While intense athletic training can cause physiological growth, moderate aerobic exercise is a valuable tool for managing pathological LVH. Activities like brisk walking, swimming, or cycling help peripheral arteries become more flexible, which lowers blood pressure. This improvement in vascular flexibility means the left ventricle doesn’t have to squeeze as hard to push out blood.
On an ECG, regular exercise often correlates with improvement in the strain pattern. However, for those with moderate left ventricular hypertrophy, it’s important to avoid heavy weightlifting or isometric exercises (like pushing against a heavy object), since these can cause sudden, significant spikes in blood pressure that may worsen mild concentric left ventricular hypertrophy.
Cutting Out Alcohol and Tobacco
Smoking and heavy alcohol use are direct contributors to thickening of the left ventricle. Tobacco smoke contains chemicals that cause immediate stiffening of the arteries, while chronic alcohol use can be toxic to heart cells themselves. Quitting these habits lets the heart operate under less stress.
In patients where lifestyle plays a role in the underlying cause, these changes can lead to visible improvement on an echo report within six months to a year. This kind of regression is a major treatment goal, since every millimeter of reduced wall thickness significantly lowers the risk of developing left atrial enlargement and subsequent atrial fibrillation.
Monitoring Progress Through Imaging
The clearest proof of successful lifestyle change shows up in follow-up imaging. A cardiologist looks for a reduction in “Left Ventricular Mass Index” on a repeat echo. If the walls are thinning and diastolic function is improving, it means the fibrosis isn’t yet permanent and the heart is regaining its elasticity. Even if LVH voltage criteria still appear on an ECG due to how electrical signals travel, the structural health of the heart is the real measure of long-term outlook.
Conclusion
Left ventricular hypertrophy is a serious condition that can develop silently but carry significant long-term consequences if left untreated. Recognizing symptoms like chest discomfort, shortness of breath, or an irregular heartbeat can help you take action early and protect your heart health. Early diagnosis allows for better management and lowers the risk of complications such as heart failure or arrhythmias.
Managing left ventricular hypertrophy usually involves addressing the underlying cause, such as controlling blood pressure or improving lifestyle habits. With proper care, including medication and regular monitoring, many people manage the condition effectively. Staying informed and proactive is key to maintaining a healthy heart and preventing further complications.
Frequently Asked Questions About Left Ventricular Hypertrophy
What is left ventricular hypertrophy?
Left ventricular hypertrophy is a condition in which the muscle of the left ventricle, the heart’s main pumping chamber, becomes thickened. This thickening can make it harder for the heart to pump blood efficiently. Over time, it may lead to reduced heart function or other complications. It’s often linked to conditions that increase the heart’s workload.
What causes left ventricular hypertrophy?
The most common cause is high blood pressure, which forces the heart to work harder over time. Other causes include heart valve diseases, especially aortic valve narrowing, along with certain genetic conditions. Long-term physical strain on the heart can also play a role. Identifying the cause is essential for proper treatment.
What are the symptoms of left ventricular hypertrophy?
Symptoms may include shortness of breath, chest pain, fatigue, dizziness, and an irregular heartbeat. Some people may not notice any symptoms in the early stages. As the condition progresses, symptoms tend to become more noticeable. Regular checkups can help catch the condition early.
Is left ventricular hypertrophy dangerous?
Yes, it can be dangerous if left untreated. It raises the risk of serious conditions like heart failure, heart attack, and arrhythmias. The thickened heart muscle can also reduce how efficiently blood flows. Early detection and management can significantly lower these risks.
How is left ventricular hypertrophy diagnosed?
Doctors diagnose it using tests like an electrocardiogram (ECG) and an echocardiogram, which provides images of the heart. These tests help assess the thickness of the heart muscle and its overall function. Additional imaging or blood tests may also be used. An accurate diagnosis is important for effective treatment planning.
How is left ventricular hypertrophy treated?
Treatment focuses on addressing the underlying cause, such as controlling high blood pressure. Medications, lifestyle changes, and regular monitoring are commonly recommended. In some cases, treating valve disease or other heart conditions may be necessary. Proper management can help prevent progression and complications.