8 Microscopic Hematuria Warning Signs That Need Attention
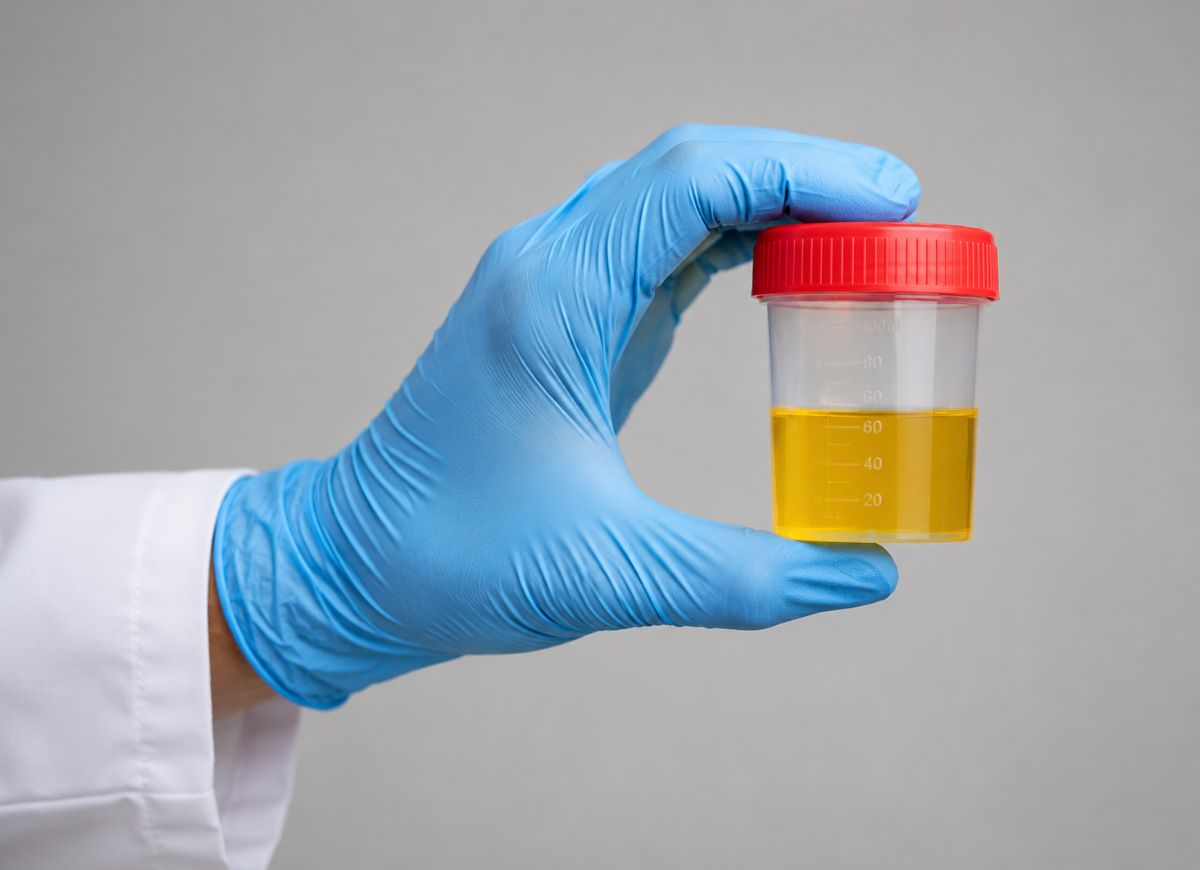
A urine test can reveal things the eyes cannot see. That’s what makes microscopic hematuria so unsettling for many people. You may feel completely normal, see no red or pink color in the toilet, and still be told there are tiny traces of blood in your urine. Suddenly, a routine checkup feels more serious than expected.
Microscopic hematuria means blood is present in the urine, but the amount is too small to notice without a microscope or lab test. Sometimes it comes from something temporary, like intense exercise, a urinary tract infection, kidney stones, menstruation contamination, or minor irritation. Other times, it may point to a condition involving the kidneys, bladder, prostate, ureters, or urinary tract.
The tricky part is that it often causes no obvious symptoms. A person may only find out after a yearly physical, pregnancy checkup, work medical exam, or test done for another reason entirely. When it does appear alongside burning during urination, pelvic pain, back pain, frequent urination, fever, cloudy urine, swelling, high blood pressure, or unexplained fatigue, it may need closer evaluation.
Below are eight warning signs that can accompany microscopic hematuria and point toward an underlying cause worth investigating.
What is Microscopic Hematuria?
Microscopic hematuria is a medical finding: red blood cells in the urine that are only visible under a microscope. It isn’t a disease itself, but a sign that something may be happening somewhere along the urinary tract, the kidneys, ureters, bladder, or urethra.
The urine looks completely normal to the naked eye, with none of the pink, red, or cola-colored tint seen in gross hematuria. The formal diagnostic threshold is generally three or more red blood cells per high-power microscopic field in a properly collected sample.
Because it’s invisible and symptom-free, it’s usually found by accident, during a routine physical, a pre-surgical screening, or a urinalysis done for an unrelated reason. That lab result then becomes a prompt for further investigation, since the underlying cause can range from entirely benign to serious.
Microscopic vs. Gross Hematuria
The key difference is visibility. Gross hematuria involves blood visible to the naked eye, turning urine light pink, bright red, or dark like tea or cola; even a small amount of blood can cause a noticeable color change, and it typically prompts someone to seek care right away.
Microscopic hematuria offers no visual clues at all. Urine looks its normal yellow or clear, and the person has no idea red blood cells are present. It’s discovered only through a dipstick test or, more definitively, microscopic examination of urine sediment. Since dipstick tests can produce false positives, microscopic analysis remains the gold standard for confirmation. Despite the different presentation, the underlying causes overlap significantly, from infections and kidney stones to glomerulonephritis and cancer, so both findings call for proper medical evaluation.
Why It’s Often Found by Accident
Because microscopic hematuria produces no symptoms and doesn’t change how urine looks, people simply don’t know it’s there. It’s almost always discovered incidentally, during an annual physical, an employment or insurance health screening, a pre-operative workup, or monitoring for a chronic condition like hypertension or diabetes. Sometimes a doctor orders a urinalysis to investigate unrelated symptoms like fatigue, and hematuria turns up unexpectedly.
Without these routine screenings, a slowly progressing condition like early kidney disease or a small bladder tumor could go unnoticed for a long time. That’s what makes the incidental discovery valuable: it turns an ordinary test into an early warning system.
The 8 Warning Signs
1. Pain during urination or pelvic pain. Burning, stinging pain while urinating (dysuria), often paired with pelvic or lower abdominal pressure, is a classic sign of a urinary tract infection. Bacteria, typically E. coli, inflame the bladder or urethra lining, making nerve endings hypersensitive and causing small blood vessels to rupture and leak into the urine. Bladder stones, prostatitis, and interstitial cystitis can cause similar symptoms.
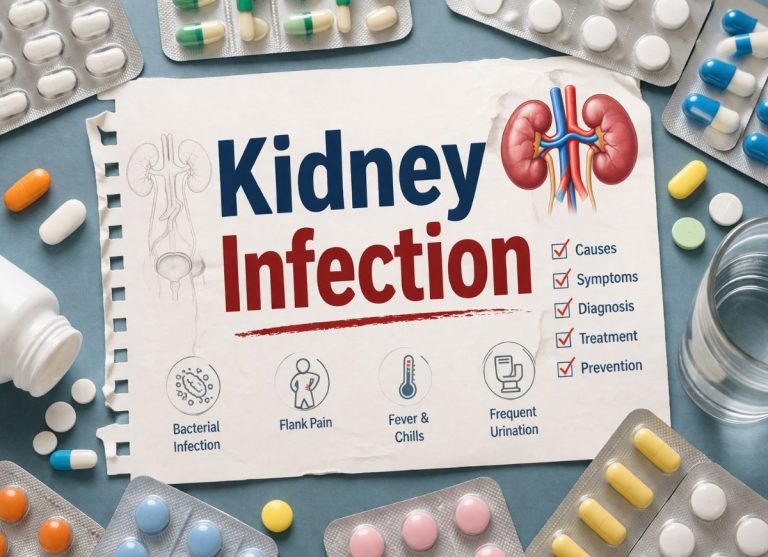
2. Flank pain. Sharp, severe pain in the side and back, between the ribs and hip, often signals a kidney problem. A kidney stone moving through the ureter causes intense, cramping “renal colic” as sharp edges scrape the lining and cause bleeding. A more constant, dull ache in the same area can point to a kidney infection (pyelonephritis), which is usually accompanied by fever, chills, and nausea and needs urgent treatment.
3. Urinary urgency and frequency. A sudden, frequent need to urinate, often producing only small amounts, typically signals bladder inflammation from an infection (cystitis). The inflamed bladder lining becomes overly sensitive and its blood vessels fragile, leading to both the urgency and the hematuria. An enlarged prostate, bladder stones, or, less commonly, bladder cancer can also cause these symptoms.
4. Fever, nausea, or chills. These systemic symptoms suggest the problem has escalated beyond the bladder, most often into a kidney infection (pyelonephritis). This is more serious than a simple bladder infection because the kidneys are highly vascular, and infection there can potentially spread into the bloodstream. The combination of these symptoms with flank pain and hematuria is a medical emergency requiring prompt antibiotic treatment.
5. High blood pressure or swelling. New hypertension paired with swelling in the legs, ankles, or around the eyes can point to kidney disease. When the kidneys’ filtering units (glomeruli) become inflamed, a condition called glomerulonephritis, they let blood cells and protein leak into the urine while also becoming less effective at removing excess salt and fluid, which raises blood pressure and causes fluid buildup in tissue. Conditions like IgA nephropathy or post-streptococcal glomerulonephritis are common culprits, and this combination usually warrants a nephrology referral.
6. Changes in the urine stream. A weak flow, trouble starting urination, or a stream that stops and starts, mostly seen in men, usually points to a bladder outlet obstruction, most commonly from an enlarged prostate (BPH). The strain of pushing urine past the obstruction can rupture fragile blood vessels on the prostate’s surface. While BPH is the usual cause, prostate cancer and urethral strictures can produce similar symptoms and need to be ruled out.
7. Unexplained fatigue. Deep, persistent tiredness alongside hematuria can point to chronic kidney disease. Healthy kidneys produce erythropoietin, a hormone that signals the body to make red blood cells; when kidney function declines, this drops, leading to anemia and fatigue. Buildup of waste products in the blood (uremia) can add to the exhaustion. Less commonly, persistent fatigue alongside hematuria can be a sign of an undiagnosed kidney or bladder cancer.
8. Unexplained weight loss. Losing a significant amount of weight (typically more than 5% of body weight over 6 to 12 months) without trying, combined with hematuria, is a red flag for a urinary tract malignancy like kidney or bladder cancer. This symptom isn’t typical of common, benign causes like UTIs or small kidney stones, so its presence calls for urgent imaging and possibly a cystoscopy.
Common Causes
Infections. UTIs, kidney infections (pyelonephritis), and prostatitis are among the most common infectious causes. Bacteria, usually E. coli, inflame the urinary tract lining, making blood vessels fragile and prone to leaking. These are typically diagnosed with a urine culture and treated with antibiotics.
Structural or obstructive issues. Kidney stones, bladder stones, and an enlarged prostate (BPH) can all cause bleeding through physical irritation or pressure changes. Stones scrape against the urinary tract lining as they move; an enlarged prostate can develop fragile blood vessels that rupture under the pressure of urination.
Kidney diseases. Conditions like IgA nephropathy, post-infectious glomerulonephritis, lupus nephritis, Alport syndrome, and polycystic kidney disease all damage the kidneys’ filtering units, allowing red blood cells to leak into urine. These are often accompanied by high blood pressure, swelling, and protein in the urine, and need specialized management by a nephrologist.
Other causes. Strenuous exercise, certain medications (blood thinners, some antibiotics, chemotherapy drugs), physical trauma, and, less commonly, cancers of the kidney, bladder, prostate, ureter, or urethra can all cause microscopic hematuria. Cancer is a less frequent cause but the most serious, which is why persistent or unexplained hematuria, especially in people over 40 or with risk factors like smoking, warrants thorough evaluation.
How It’s Diagnosed
The process usually starts with a urinalysis, checking for red blood cells, white blood cells, or protein under a microscope. If infection is suspected, a urine culture identifies the specific bacteria. A blood test for creatinine helps assess kidney function. A cystoscopy lets a urologist directly examine the urethra and bladder lining for tumors, stones, or inflammation. Imaging, an ultrasound, CT scan, or occasionally an MRI, can reveal structural problems, stones, or masses.
Transient vs. Persistent Hematuria
Transient hematuria is a temporary, one-time occurrence, often linked to benign causes like exercise, sexual intercourse, minor injury, or a short-lived UTI. It typically resolves once the trigger is removed and a repeat urinalysis comes back clear.
Persistent hematuria means red blood cells show up on two or more urinalyses over several weeks. This ongoing pattern suggests a more chronic condition that isn’t resolving on its own and typically calls for a fuller workup.
Who’s at Higher Risk
Risk factors include being over 50 (linked to bladder cancer and, in men, BPH), being male (higher risk of bladder, kidney, and prostate issues), and having a personal or family history of kidney disease, such as polycystic kidney disease, Alport syndrome, or a family history of kidney stones. A recent bacterial or viral infection, like a sore throat that precedes post-streptococcal glomerulonephritis, can also trigger temporary hematuria.
Microscopic Hematuria in Athletes
Exercise-induced hematuria is well documented in athletes doing high-intensity or endurance sports. Likely causes include repetitive bladder trauma from the bladder walls slapping together during high-impact activity, temporary changes in kidney filtration from physical stress, or dehydration irritating the urinary tract. It’s often benign, but should never be assumed normal without evaluation. Doctors typically repeat the urinalysis after 48 to 72 hours of rest; if the hematuria clears, it supports a benign, exercise-related cause. If it persists, or if other risk factors are present, a full urological workup is needed.
Frequently Asked Questions
Is microscopic hematuria serious?
It can be harmless, but shouldn’t be ignored. It’s sometimes linked to exercise, dehydration, infection, or minor irritation, but can also point to kidney disease, bladder or prostate issues, or, less commonly, cancer. Persistent findings, or ones paired with pain, fever, swelling, or urinary changes, should be checked further.
How many red blood cells define microscopic hematuria?
Generally, 3 or more red blood cells per high-power field on a properly collected urine sample, confirmed by microscopic examination rather than dipstick alone.
Can dehydration cause it?
Not drinking enough water can concentrate and irritate the urinary tract, but dehydration isn’t always a direct cause. If hydrating and repeating the test clears the finding, it may have been temporary; if it persists, further evaluation is warranted.
What cancers can cause it?
Bladder, kidney, ureter, urethral, and, in some men, prostate cancer. Most people with microscopic hematuria don’t have cancer; risk depends on age, smoking history, and whether the blood persists or comes with other symptoms.
How common is it?
Fairly common. Estimates for asymptomatic microscopic hematuria range from about 5% to 20%, with some broader reviews citing 2.4% to 31.1%. A single abnormal result shouldn’t cause panic, but persistence and risk factors matter.
Why would I have hematuria with no infection?
Kidney stones, recent exercise, trauma, menstruation contamination, prostate enlargement, kidney inflammation, certain medications, or structural issues can all cause it without a UTI being involved.
What’s the diagnostic criteria?
Three or more red blood cells per high-power field on microscopic evaluation of a properly collected sample; dipstick testing alone isn’t sufficient.
When should someone be referred to a specialist?
When hematuria persists or returns, or when risk factors are present, such as older age, smoking history, visible blood, high RBC counts, irritative urinary symptoms, or a family history of urinary tract cancers. Signs of kidney involvement, like protein in the urine, high blood pressure, or swelling, also warrant referral.
The Bottom Line
Microscopic hematuria can feel unsettling because it reveals something invisible. Your urine may look completely normal, yet a lab test shows hidden blood. In many cases the cause is temporary or treatable, like exercise, infection, stones, or irritation. Still, repeated or unexplained results deserve attention. The right response isn’t panic, but follow-up: a repeat urine test, a symptom review, and proper evaluation can help identify whether the blood is coming from the kidneys, bladder, prostate, or elsewhere in the urinary tract. Hidden blood isn’t a diagnosis. It’s a signal worth listening to early.