Cerebral Amyloid Angiopathy: Causes, Symptoms, and Brain Bleeding Risk
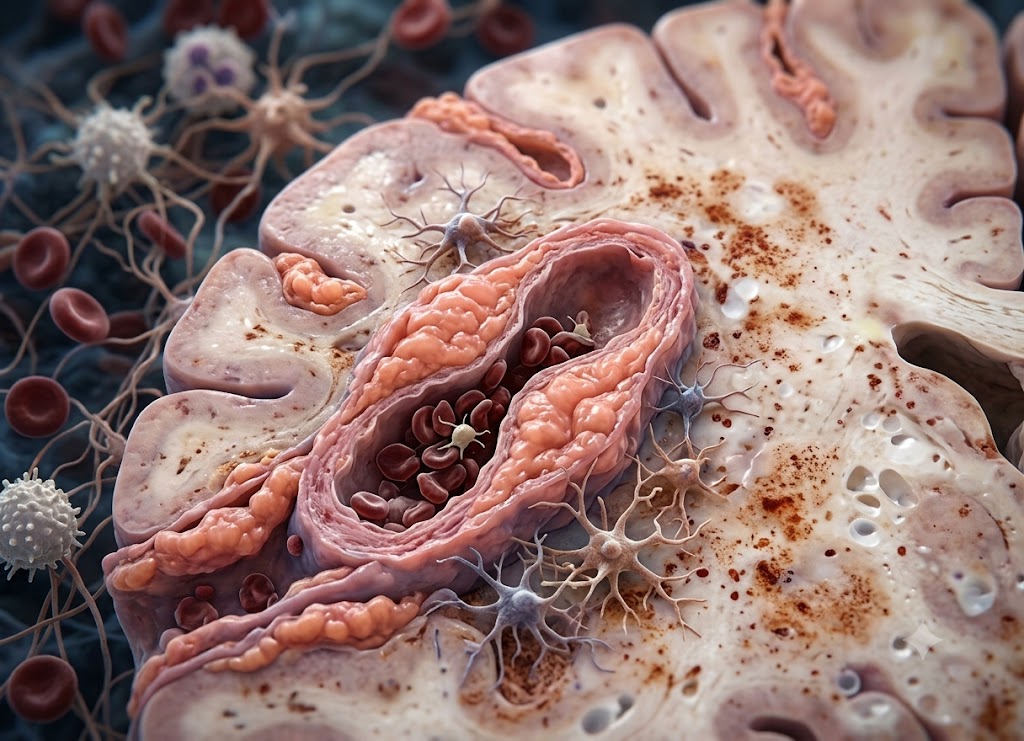
Cerebral amyloid angiopathy (CAA) is a condition in which a protein called amyloid slowly collects in the walls of small and medium-sized blood vessels in the brain. As the deposits grow, the vessels become weak and may leak or burst. CAA mostly affects older adults and is a leading cause of lobar intracerebral hemorrhage, which is bleeding in the outer parts of the brain. It can also cause tiny hidden bleeds, changes in thinking, and short stroke-like episodes.
This matters because the first clear sign of CAA is sometimes a brain bleed. Warning signs include sudden weakness, a severe headache, confusion, vision changes, trouble speaking, seizures, and problems with thinking or memory.
Some people learn they have CAA when an MRI shows microbleeds or superficial siderosis. Others find out after a larger hemorrhage. This article covers the causes, symptoms, and bleeding risk of CAA, and explains why early recognition and careful medical care matter.
Overview of Vascular Protein Accumulation
To understand CAA, it helps to see how proteins can build up in the brain. CAA is a disorder of the brain’s blood vessels. Amyloid-beta protein gradually collects in the walls of small and medium-sized arteries and capillaries in the cerebral cortex and the brain’s outer lining (the leptomeninges).
Amyloid-beta is produced → the brain fails to clear it → it deposits in vessel walls → the vessels weaken
These hard, insoluble deposits change the structure of the vessels, leaving them brittle and easy to rupture. This is a common change in the aging brain, and it is a major cause of cognitive decline and spontaneous bleeding inside the head.
CAA is different from Alzheimer’s disease, where amyloid forms plaques in the brain tissue itself. In CAA, the protein settles inside the vessel walls. Some people have no obvious symptoms, while others develop serious complications, so knowing the warning signs is important for getting medical help in time.
Pathophysiology and Structural Vessel Damage
The root problem in CAA is that the brain becomes poor at clearing its own waste. Amyloid-beta builds up in the middle and outer layers of the vessel walls and gradually destroys their strength.
                    [Vascular Pathological Cascade]
                                   │
     ┌─────────────────────────────┴─────────────────────────────┐
     ▼                                                           ▼
[Smooth Muscle Displacement]                        [Fibrinoid Necrosis & Leaks]
 ├── Loss of structural elasticity                   ├── Severe degradation of tissue
 ├── Formation of microaneurysms                     ├── High risk of spontaneous rupture
 └── Impaired pressure autoregulation                └── Blood-brain barrier breakdown
In simple terms, the amyloid fibers push aside the healthy muscle cells in the vessel wall. Without them, the vessel can no longer widen or narrow safely when blood pressure changes.
As CAA advances, the damaged wall may be replaced by a fragile, uniform material, a process called fibrinoid necrosis. Sometimes the buildup also triggers an inflammatory reaction known as CAA-related inflammation, which can cause sudden neurological changes.
Over time the blood-brain barrier breaks down. Fluid leaks into nearby tissue and causes changes in the deep white matter. Or the wall simply gives way under normal pressure, causing a sudden stroke or lobar hemorrhage.
Sporadic vs. Familial Typologies
Doctors divide CAA into two groups based on where it comes from: the common sporadic form and the much rarer familial form.
[Sporadic Form]  ──► Linked to advancing age and APOE alleles; non-hereditary patterns
[Familial Form]  ──► Autosomal dominant mutations (APP gene); early onset in 40s or 50s
The sporadic variant. This is by far the most common type, and it becomes more likely with age. It often appears alongside Alzheimer’s changes in older people, but it can also occur alone. Age is the biggest risk factor, and certain APOE gene variants raise both the chance of CAA and the severity of bleeding.
The hereditary variant. Familial CAA is very rare. It is caused by autosomal dominant mutations, most often in the amyloid precursor protein (APP) gene. These mutations make the body produce too much amyloid-beta, or a stickier form that clumps quickly in the vessels. People with this form usually get symptoms much earlier, often in their 40s or 50s, and face repeated brain bleeds and fast-moving dementia. Well-known examples are the Dutch, Icelandic, and Flemish types.
Modern Diagnostics and Clinical Distinctions
In the past, a firm diagnosis meant examining brain tissue under a microscope. Today, doctors can diagnose CAA without surgery by using advanced imaging, mainly MRI.
[T2*-Weighted Gradient Echo MRI] ──► Identifies Cortical Microbleeds ──► Confirms Probable CAASequences such as susceptibility-weighted imaging can reveal tiny dark spots, called microbleeds, along the outer edges of the brain. One point is worth clarifying. Angioplasty does not exist as a treatment for CAA, because angioplasty is used for blockages in large arteries, not for fragile small vessels full of protein. Still, identifying CAA on imaging is very useful. It helps doctors manage blood pressure carefully and avoid blood thinners that could do harm.
Early Symptoms of Cerebral Amyloid Angiopathy
The early symptoms of CAA are often mild and vary a lot from person to person. Common ones are brief neurological episodes (called TFNEs), slow decline in thinking, and new headaches. Because these signs are so nonspecific, diagnosis can be difficult.
Unlike a major stroke, which hits suddenly and severely, CAA often begins quietly. A person may have short spells of tingling or numbness in a limb, or brief weakness that clears completely within minutes. These “amyloid spells” can repeat in the same way each time. Meanwhile, some people notice their mental sharpness fading, especially planning, organizing, and multitasking. This is often written off as normal aging at first.
New headaches can also be an early sign, sometimes linked to inflammation around the affected vessels. Because these early symptoms are so varied, doctors need to stay alert when an older adult has new, unexplained neurological events.
Early Presentations and “Amyloid Spells”
Early CAA signs are usually subtle, short-lived, and different from one person to the next. Unlike a sudden ischemic stroke, CAA tends to creep in.
The most typical warning signs are transient focal neurological episodes (TFNEs), or “amyloid spells.” These are brief, repeated episodes of disturbed brain function that last a few minutes and then clear up fully.
                    [TFNEs vs. Standard Ischemic TIAs]
                                       │
     ┌─────────────────────────────────┴─────────────────────────────────┐
     ▼                                                                   ▼
[Amyloid Spells (TFNEs)]                                [Ischemic Mini-Strokes (TIAs)]
 ├── Driven by localized cortical irritation             ├── Driven by temporary arterial blockages
 ├── Features "positive" symptoms (spreading tingling)   ├── Features "negative" symptoms (sudden drop)
 └── High risk of hemorrhage if mistreated               └── Requires immediate antiplatelet therapy
Amyloid spells often involve added sensations rather than lost ones. People describe numbness or tingling that slowly spreads along a limb, or visual disturbances like flashing or shimmering lights.
These episodes come from irritation of the brain’s surface. The cause may be tiny bleeds, small seizures, or temporary spasms in vessels damaged by amyloid.
Executive Decline and Vascular Headaches
As CAA quietly progresses, it brings clear changes in thinking and physical health, reflecting ongoing damage to the brain’s smallest vessels.
Progressive executive decline. The thinking problems in CAA can look different from typical Alzheimer’s. Memory may be affected, but the bigger difficulties are usually with planning, organizing, multitasking, and processing speed. This pattern comes from the combined effect of many microbleeds and white matter changes, which disturb the pathways that connect different brain areas.
New-onset headaches and neurological irritation. A new, lasting headache in an older adult can point to vessel problems. In CAA-related inflammation, headaches may become severe and centered on one area. People may also have unsteady walking, dizziness, or sudden seizures with no obvious trigger. All of these come from blood products slowly leaking and irritating the brain’s surface.
High-Risk Diagnostic Mimics in Older Adults
A major challenge is that CAA symptoms are easily confused with more common conditions. Misdiagnosis is frequent, and it can lead to dangerous treatment choices.
                      [The Dangerous Diagnostic Crossroad]
                                          │
    ┌─────────────────────────────────────┼─────────────────────────────────────┐
    ▼                                     ▼                                     ▼
[Transient Ischemic Attacks]     [Late-Onset Migraines]                [Alzheimer's Dementia]
 ├── Mistaken for blood clots     ├── Mistaken for benign aura          ├── Mistaken for pure tau/plaque
 └── Blood thinners prescribed     └── True vascular vulnerability       └── Shared cognitive overlap
          │                                     │                                     │
          └─────────────────────────────────────┼─────────────────────────────────────┘
                                                ▼
                         [High Risk of Major Intracerebral Hemorrhage]
All three paths can end in a serious intracerebral hemorrhage.
Transient ischemic attacks (TIAs). Amyloid spells cause short-lived symptoms, so they are often labeled as ordinary TIAs. That is risky. Standard TIA treatment uses antiplatelet or anticoagulant drugs to thin the blood. In someone with CAA, these drugs can make the fragile vessels burst and cause a major brain bleed.
Migraines with aura. Spreading numbness or flashing lights during an amyloid spell can look just like a migraine aura. When an older person has these symptoms for the first time, it may be called a late-life migraine, especially if a headache comes with it.
Late-onset epilepsy. Focal seizures can cause brief movement and sensation changes that look the same as TFNEs. Leaked blood products and iron deposits on the brain surface irritate the cortex, so CAA itself is a direct cause of late-onset epilepsy, which makes the picture even more confusing.
Alzheimer’s disease. Telling CAA-related decline apart from Alzheimer’s is hard, mostly because the two often exist together in the aging brain. CAA tends to affect planning and processing speed first, rather than memory recall. Still, a confirmed diagnosis needs advanced imaging that shows the typical bleeding markers.
What is the Brain Bleeding Risk with Cerebral Amyloid Angiopathy?
The bleeding risk in CAA is significant. It is one of the main causes of spontaneous lobar intracerebral hemorrhage (ICH) in older people, and it also produces ongoing small bleeds called cerebral microbleeds.
Mechanisms of Vascular Rupture and Lobar Hematomas
CAA is a major cause of brain bleeds that happen on their own, without an injury and without high blood pressure being the cause, in older adults.
The risk comes directly from the wearing down of the vessel walls. Amyloid-beta gathers in the middle layer of the cortical and leptomeningeal arteries and destroys the smooth muscle cells there.
[Amyloid-Beta Accumulation] ──► Smooth Muscle Loss ──► Fibrinoid Necrosis ──► Normal BP Pulse ──► RuptureWithout these muscle cells, arteries lose their stretch and their ability to handle pressure changes. As the disease advances, fibrinoid necrosis replaces healthy wall tissue with a brittle material that has almost no strength.
As a result, even everyday shifts in blood pressure can tear these vessels. When one ruptures, blood spills into the surrounding brain and forms a pocket called a hematoma.
CAA mainly affects the small and medium arteries that supply the outer lobes, so these bleeds usually happen near the brain’s surface. This lobar location is a key clue that helps neurologists tell CAA apart from the deep brain bleeds usually caused by long-term high blood pressure.
The Hemorrhagic Spectrum: From Microscopic Leaks to Major Bleeds
CAA shows up on brain scans as three kinds of bleeding. Together they help doctors judge how severe the disease is and how likely larger bleeds are in the future.
                  [The CAA Hemorrhagic Continuum]
                                 │
     ┌───────────────────────────┼───────────────────────────┐
     ▼                           ▼                           ▼
[Lobar Intracerebral Bleeds]  [Cerebral Microbleeds]     [Cortical Superficial Siderosis]
 ├── Large, acute hematomas   ├── Tiny, chronic dots     ├── Linear iron tracking
 ├── Triggers severe deficits ├── Asymptomatic on check  ├── Traces brain grooves
 └── High recurrence rates    └── Gauges vessel decay    └── Signals extreme bleed risk
Lobar intracerebral hemorrhage (ICH). This is the most severe form of CAA bleeding. Large bleeds occur in the brain’s lobes (frontal, parietal, temporal, or occipital), typically where grey and white matter meet. They cause sudden, serious problems tied to the affected brain area, and they are likely to happen again.
Cerebral microbleeds (CMBs). These are pinhead-sized leaks, usually 2 to 10 millimeters across. One alone rarely causes symptoms. But finding several spread across the outer lobes on an MRI is a classic sign of advanced vessel damage.
Cortical superficial siderosis (cSS). On scans, this appears as thin, dark lines of iron tracing the deep folds of the brain’s surface. These are leftovers from earlier small leaks into the spaces around the brain. Like microbleeds, they are an important sign in diagnosing CAA and point to advanced vessel weakness and a high chance of future major bleeding.
Clinical Stratification and Antithrombotic Management
The danger of a major bleed is not the same for everyone. It depends on what shows up on imaging, on genetic markers, and on which medicines a person takes.
[Pre-Existing Lobar Microbleeds + APOE ε4 Allele] ──► Severe Vascular Weakness ──► High Recurrence RiskAn older person’s risk of a CAA-related stroke or major lobar bleed goes up with the number of microbleeds and iron tracks on their MRI. Genetics adds more information: carrying the APOE ε2 or ε4 variants is strongly linked to more frequent repeat bleeds in CAA.
A big challenge is the use of antithrombotic drugs, meaning blood thinners and antiplatelets such as aspirin. Doctors commonly prescribe these to older adults with heart conditions or clot risks.
However, if someone has CAA that hasn’t been diagnosed, these drugs can make the fragile vessels bleed heavily and turn small leaks into life-threatening hemorrhages. That is why finding these vessel changes early is so important. It lets doctors weigh a patient’s heart and clot risks against the danger of a severe brain bleed.
The Diagnostic and Prognostic Considerations for CAA
Diagnosing CAA combines a clinical check-up with advanced imaging. The outlook depends mainly on how likely repeat brain bleeds are and on how much thinking ability is lost. It also helps to understand how CAA is diagnosed without surgery, how it is managed, and how it differs from related conditions like Alzheimer’s disease.
Application of the Modified Boston Criteria
A definite diagnosis once required a sample of brain tissue, taken by biopsy or after death, to see the protein deposits directly. A biopsy carries real risks, so doctors now use the modified Boston Criteria for a non-invasive diagnosis.
                                  [Modified Boston Criteria Protocols]
                                                 │
       ┌─────────────────────────────────────────┼─────────────────────────────────────────┐
       ▼                                         ▼                                         ▼
[Patient Demographic Threshold]        [Advanced MRI Sequences]                  [Key Hemorrhagic Identifiers]
 ├── Age limit strictly > 50            ├── GRE (Gradient-Recalled Echo)         ├── Multiple strictly lobar microbleeds
 └── Spontaneous lobar hemorrhage       └── SWI (Susceptibility-Weighted)        └── Cortical superficial siderosis (cSS)
These guidelines combine a person’s medical history with findings from a brain MRI. Radiologists use sequences that are very sensitive to iron and blood products, such as GRE and SWI.
If a person over 50 has a spontaneous lobar hemorrhage, and their MRI shows multiple microbleeds strictly in the outer lobes or cortical superficial siderosis, with no other clear cause, they can be diagnosed with “probable CAA.” This approach lets neurologists spot weakened vessels early and adjust care without surgery.
Clinical Care and Blood Pressure Regulation
At present, CAA has no cure, and no treatment can clear amyloid once it is in the vessel walls. Since the damage can’t be reversed, care focuses on lowering the chance of future bleeds and handling related problems.
                 [Vascular Management Guidelines]
                                     │
     ┌───────────────────────────────┴───────────────────────────────┐
     ▼                                                               ▼
[Aggressive Autoregulation Support]                  [Antithrombotic Risk Analytics]
 ├── High-precision blood pressure targets            ├── Strict review of anticoagulant use
 ├── Targets strictly below 130/80 mmHg               ├── High risk of transforming minor leaks
 └── Reduces mechanical stress on weak walls          └── Weighs stroke prevention vs. brain bleeds
Strict blood pressure control. This is the most important step. High blood pressure puts extra strain on already brittle vessel walls and makes a rupture more likely. Doctors use blood pressure medicines to reach tight targets, usually below 130/80 mmHg.
Careful review of blood thinners. Decisions about these drugs must be made case by case. Aspirin and direct oral anticoagulants are often prescribed for conditions like atrial fibrillation or coronary artery disease. In CAA, though, they can turn small, silent leaks into large, dangerous bleeds. Doctors must weigh the risk of clots against the serious danger of a brain hemorrhage.
Managing other symptoms. If leaking blood irritates the brain surface and causes seizures, doctors prescribe anti-seizure medicine. After a major bleed, physical rehabilitation and stroke support help people recover and stay independent.
Structural Comparison: CAA vs. Alzheimer’s Disease
CAA and Alzheimer’s disease are separate diagnoses, but they share one process: abnormal buildup of amyloid-beta. The key difference is where in the brain the protein collects.
[Alzheimer's Disease]  ──► Parenchymal space (extracellular senile plaques) ──► Widespread dementia
[Amyloid Angiopathy]   ──► Cortical/leptomeningeal blood vessel walls       ──► Spontaneous hemorrhages
In CAA, amyloid-beta builds up inside the walls of small and medium arteries in the cortex and the thin membranes covering the brain. This weakens the vessels until they rupture, causing lobar hemorrhages, transient spells, and microbleeds.
In Alzheimer’s, amyloid-beta collects in the working tissue of the brain (the parenchyma) as senile plaques outside the cells. Together with tangles of tau protein inside the cells, these plaques disrupt communication between neurons and cause inflammation and cell death. The result is progressive memory loss and cognitive decline.
The two conditions overlap a great deal. Autopsy studies show that up to 90% of people with Alzheimer’s also have some degree of CAA. This can produce a mixed picture, with gradual memory loss alongside sudden bleeds, and it makes diagnosis and long-term care more complicated.
Apolipoprotein Alleles and Genetic Risk Profiles
Genes strongly influence a person’s baseline risk and the severity of the sporadic form of CAA. The most important gene is Apolipoprotein E (APOE), which helps transport cholesterol and clear waste like amyloid-beta from the brain.
               [APOE Allelic Risk Stratification]
                                  │
     ┌────────────────────────────┴────────────────────────────┐
     ▼                                                         ▼
[The ε4 Allele Variant]                                   [The ε2 Allele Variant]
 ├── Drives high overall amyloid burdens                   ├── Structurally weakens vessel walls
 ├── Increases risk of Alzheimer's tissue plaques          ├── Neutral/protective against Alzheimer's
 └── Accelerates protein build-up in blood vessels         └── Strongly tied to recurrent lobar bleeds
Genetic risk variation. The ε3 allele is considered neutral, while inheriting the ε2 or ε4 variants significantly changes a person’s vessel risk.
The ε4 allele, a well-known Alzheimer’s risk factor, also raises the risk of amyloid changes in vessels by speeding up protein buildup in both brain tissue and blood vessels.
The ε2 allele has a more specific link to bleeding. Although it is generally neutral or even protective against Alzheimer’s plaques, it causes real weakness in vessel walls. People who carry ε2 therefore face a much higher risk of repeat CAA-related strokes and large lobar hemorrhages.
Beyond these common sporadic risk factors, rare inherited forms of CAA come from direct autosomal dominant mutations in the amyloid precursor protein (APP) gene. These cause an aggressive, early-onset disease that runs in families and can lead to major brain bleeds in a person’s 40s or 50s.
Conclusion
Cerebral amyloid angiopathy weakens the blood vessels of the brain and raises the risk of bleeding. It is most common with aging and can bring cognitive decline, brief neurological episodes, microbleeds, and lobar intracerebral hemorrhage.
Its symptoms can look like stroke, dementia, migraine, or seizure disorders, so a proper neurological exam and brain imaging are important. Sudden weakness, trouble speaking, severe headache, confusion, vision loss, seizure, or loss of consciousness should always be treated as an emergency.
Frequently Asked Questions
1. What is cerebral amyloid angiopathy?
CAA is a condition in which amyloid protein builds up in the walls of the brain’s blood vessels. The deposits make the vessels fragile and more likely to leak or bleed. It mostly affects older adults, though rare inherited forms can start earlier. CAA is a recognized cause of brain bleeding and can also contribute to cognitive decline.
2. What causes cerebral amyloid angiopathy?
CAA is usually caused by age-related buildup of amyloid-beta in the small and medium blood vessels of the brain. Why the buildup happens is not always clear. Some cases are linked to Alzheimer’s disease, while others occur without obvious dementia. Rare inherited forms may be linked to specific gene changes.
3. What symptoms can cerebral amyloid angiopathy cause?
Symptoms can include sudden weakness, numbness, confusion, trouble speaking, vision changes, severe headache, seizures, or loss of consciousness if bleeding occurs. Some people have short stroke-like episodes that come and go. Others develop gradual memory problems, slower thinking, or trouble with attention. In some cases, CAA is found on an MRI before any clear symptoms appear.
4. Why does cerebral amyloid angiopathy increase brain bleeding risk?
Amyloid deposits weaken the walls of the brain’s blood vessels. These fragile vessels may leak small amounts of blood or rupture and cause a larger hemorrhage. Bleeding often occurs in the lobar areas of the brain, such as the frontal, parietal, temporal, or occipital lobes. Blood thinners, uncontrolled blood pressure, and falls can add extra risk for some patients.
5. How is cerebral amyloid angiopathy diagnosed?
Diagnosis usually relies on brain imaging, especially MRI, to look for patterns such as lobar microbleeds or superficial siderosis. CT scans may be used in emergencies to spot active bleeding. Doctors also review symptoms, age, medical history, medications, and other possible causes of the bleed. In most living patients, the diagnosis rests on clinical and imaging criteria rather than a brain biopsy.