7 Tests Doctors Use to Diagnose Fibromyalgia Disease And How They Use Them
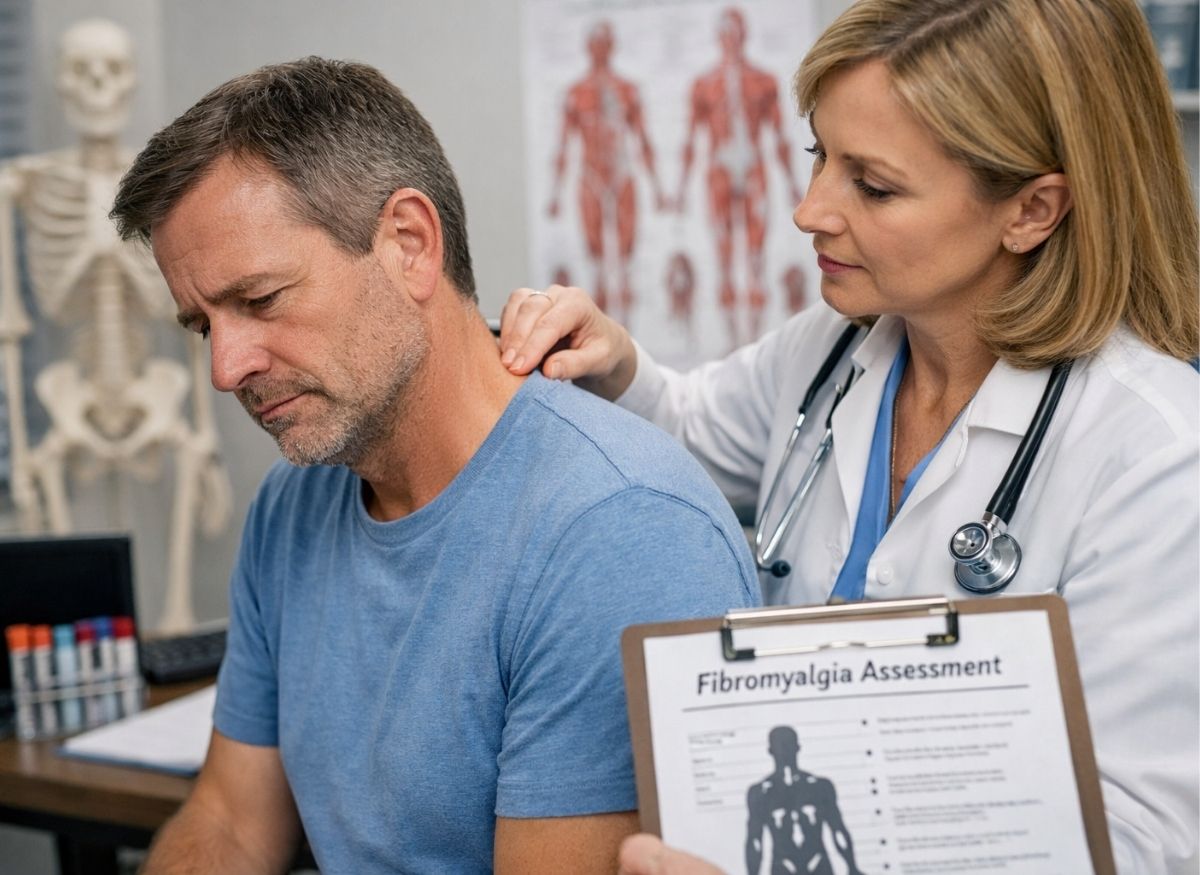
Fibromyalgia is among the most misunderstood and hard-to-diagnose conditions in modern medicine. Many people live for years with ongoing pain, exhaustion, and brain fog without clear answers, and are often told nothing is wrong or that it’s just stress. The difficulty is that the condition doesn’t appear on standard lab tests or imaging, so diagnosis depends on clinical evaluation rather than one definitive test.
For that reason, doctors combine several methods to identify fibromyalgia and exclude other conditions with similar symptoms. These tests aren’t meant to “prove” fibromyalgia directly. They exist to eliminate other possible causes and build a full clinical picture. The process can be frustrating and confusing, especially when results come back normal despite continuing symptoms.
This article covers 7 key assessments doctors use, how each one works, and, just as importantly, what they may miss. Understanding the process can help you navigate diagnosis with more confidence and see why fibromyalgia is so often overlooked or delayed.
Tests Used in a Fibromyalgia Diagnosis
Diagnosing fibromyalgia takes a comprehensive, structured approach rather than a single test. Because it produces no clear abnormalities on standard labs or imaging, doctors rely on a mix of symptom evaluation, physical examination, and exclusion of other medical conditions.
This multi-step process makes sure the symptoms aren’t caused by other disorders such as autoimmune disease, thyroid dysfunction, or neurological conditions. Knowing how the tests work explains why diagnosis can take time and demands careful clinical judgment.
The 2016 ACR Criteria
The most widely accepted method is the 2016 criteria from the American College of Rheumatology. It is considered the current clinical standard and looks at both how widespread the pain is and how severe the related symptoms are.
Earlier models leaned heavily on tender point exams. The 2016 criteria give a fuller picture by including fatigue, sleep disturbance, and cognitive problems alongside pain, reflecting the condition’s complex, multi-system nature. To meet the criteria, symptoms must have been present at a similar level for at least three months, and other possible medical causes must be ruled out.
How the Widespread Pain Index and Symptom Severity Scale Work
Diagnosis rests on two scoring systems: the Widespread Pain Index (WPI) and the Symptom Severity (SS) scale. The WPI counts how many body areas have been painful over the past week, across up to 19 regions. A higher score means more extensive pain, a core feature of fibromyalgia.
The SS scale rates the intensity of key symptoms such as fatigue, waking unrefreshed, and cognitive difficulty, and also accounts for other physical symptoms. It reflects how severely the condition affects overall function. A diagnosis is typically confirmed when one of these combinations is met:
- A WPI of 7 or higher together with an SS score of 5 or higher
- A WPI of 4 to 6 together with an SS score of 9 or higher
Using both scores ensures that the spread of pain and the severity of symptoms are weighed together, giving a more accurate picture.
Why These Criteria Matter
The 2016 criteria have greatly improved how fibromyalgia is diagnosed. By moving beyond tender points and considering the full range of symptoms, they allow earlier and more consistent diagnosis.
They also let primary care providers recognize fibromyalgia without specialized testing. That matters because early recognition can lead to better symptom management and quality of life.
The 7 Key Assessments
Diagnosis combines structured assessments with exclusionary tests rather than one definitive exam. Since fibromyalgia doesn’t show clearly on standard lab or imaging tests, doctors use several evaluation methods to build the full picture. These seven assessments work together to confirm fibromyalgia while ruling out conditions with similar symptoms.
- Widespread Pain Index (WPI) assessment. One of the most important tools. It measures how many body areas have hurt over the past week. Patients identify pain in up to 19 specific regions, with each area scoring one point. A higher score means more widespread pain, a defining trait of fibromyalgia.
- Symptom Severity (SS) scale evaluation. This gauges how intensely the condition affects daily life, focusing on fatigue, unrefreshing sleep, and cognitive difficulties, plus other physical symptoms. It shows doctors not only where pain occurs but how much it affects overall function.
- Detailed symptom history. Doctors assess when symptoms began, how long they’ve lasted, and how they fluctuate. Symptoms must be present for at least three months. This step also reveals patterns typical of fibromyalgia, such as widespread pain combined with fatigue and cognitive problems.
- Physical examination. Performed to rule out other causes of pain. Doctors check for signs of inflammation, joint abnormalities, or neurological problems. Unlike older methods, modern evaluation doesn’t rely only on tender points. The exam looks for features that might point to a different diagnosis.
- Blood tests to exclude other conditions. Labs may check inflammation markers, thyroid function, vitamin levels, and autoimmune indicators. Rheumatoid arthritis, lupus, and thyroid disorders can mimic fibromyalgia, so ruling them out is essential.
- Imaging for structural causes. X-rays, MRI, or CT scans may be used to exclude structural problems that could explain chronic pain. They don’t diagnose fibromyalgia directly, but they help confirm the symptoms aren’t due to arthritis, spinal disorders, or nerve compression.
- Mental health evaluation. Often included because anxiety and depression frequently overlap with fibromyalgia, each able to influence and be influenced by chronic pain. Assessing mental health helps doctors see the whole picture and address every contributing factor in a comprehensive plan.
The WPI gives a structured way to quantify where pain occurs. Counting the affected regions helps separate fibromyalgia from more localized pain conditions.
It covers areas across the whole body, so pain is assessed in many regions rather than just one, and that broad distribution is a hallmark of fibromyalgia. Combined with the SS scale, the WPI forms the foundation of modern diagnostic criteria, letting clinicians assess both the extent of pain and the impact of symptoms for a more accurate, consistent diagnosis.
How the Symptom Severity Scale Is Evaluated
The SS scale is a key part of diagnosis, designed to measure how intensely symptoms affect daily life beyond pain alone. The WPI asks where pain occurs, while the SS scale asks how severe the core symptoms are and how much they limit function.
This two-part scoring gives a fuller view, making sure fatigue, sleep problems, and cognitive issues are weighed alongside physical pain. The final score runs from 0 to 12 and is used with the WPI to confirm a diagnosis.
Part one: core symptom severity. The first part covers three defining symptoms: fatigue, waking unrefreshed, and cognitive difficulties often called “fibro fog.” Each is rated for severity over the past week on a 0 to 3 scale, where 0 means absent and 3 means severe, persistent problems that significantly interfere with daily life. The three scores are added into a subtotal from 0 to 9, showing how deeply the condition affects energy, sleep quality, and mental clarity.
Part two: additional somatic symptoms. The second part looks at other physical symptoms commonly associated with fibromyalgia, such as headaches, digestive issues like irritable bowel symptoms, dizziness, or numbness and tingling. Rather than scoring each symptom, it measures the overall burden, giving a score of 0 to 3 depending on how many are present and how widespread. This ensures fibromyalgia is recognized as a multi-system condition, not just a pain disorder.
How the final score supports diagnosis. The total SS score combines both parts. It reflects overall symptom severity and plays a crucial role in confirming the diagnosis. The thresholds depend on the WPI: a score of at least 5 is needed when pain is widespread, while a higher score is required if pain is less extensive. This grounds the diagnosis in the full clinical picture, physical and functional.
The SS scale matters because it captures aspects that are often overlooked, such as fatigue and cognitive dysfunction. These can be as disabling as pain yet don’t appear on traditional medical tests.
Including them makes the diagnosis more accurate and patient-centered. It reflects how the condition truly affects daily life and helps doctors build more effective, personalized management plans.
Other Factors That Influence a Diagnosis
Diagnosis goes beyond standard assessments and needs a broader clinical view. The WPI and SS scale are the foundation, but several other factors are critical to an accurate diagnosis.
These include ruling out similar conditions, recognizing overlapping disorders, considering patient history, and applying up-to-date criteria. Because fibromyalgia shares symptoms with many other chronic illnesses, careful, holistic evaluation is essential to avoid misdiagnosis and ensure proper treatment.
How Fibromyalgia Differs From Chronic Fatigue Syndrome
One of the most important tasks is distinguishing fibromyalgia from look-alike conditions, particularly myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS).
Both involve fatigue, cognitive difficulty, and sleep disturbance, but their defining features differ. Recognizing this helps doctors avoid confusion and give patients the most appropriate diagnosis.
The central role of pain in fibromyalgia. The defining feature is widespread musculoskeletal pain, present across multiple body areas and persisting over time. Diagnosis depends heavily on how the pain is distributed and how it interacts with fatigue and cognitive dysfunction. Without widespread pain, a fibromyalgia diagnosis is unlikely.
The defining feature of ME/CFS. ME/CFS is defined by post-exertional malaise (PEM), a delayed and often severe worsening of symptoms after physical or mental effort. In fibromyalgia, activity may increase discomfort but remains manageable, whereas PEM can cause a significant, prolonged decline in function. This difference is critical.
Key differences in symptom patterns. Both involve fatigue and cognitive issues, but the pattern and intensity differ. In fibromyalgia, pain is constant and widespread, with fatigue a major but secondary symptom. In ME/CFS, fatigue dominates and PEM is required for diagnosis. The response to activity is also more extreme, often producing delayed crashes lasting days or longer.
Telling the two apart is essential for proper diagnosis and treatment, since mistaking one for the other can lead to ineffective management and prolonged frustration.
By carefully evaluating symptom patterns, doctors can distinguish them and tailor care, which shows why a thorough, individualized diagnostic process matters.
The FM/a Test
The FM/a test is a specialized blood test developed to identify fibromyalgia by analyzing immune system activity. It measures cytokines and chemokines, signaling proteins involved in inflammation and immune responses.
The idea is that people with fibromyalgia may have a distinct immune response pattern compared with healthy individuals or those with conditions like rheumatoid arthritis or lupus. The test produces a score from 1 to 100, with higher values suggesting a greater likelihood of fibromyalgia. Although the concept is promising, the FM/a test is not currently accepted as a standard diagnostic tool.
Medical Specialists Involved in Diagnosis
Diagnosis often needs input from several specialists. Because symptoms overlap with many other conditions, alternative causes must be ruled out before a diagnosis is confirmed.
The rheumatologist. Typically the primary specialist. Rheumatologists focus on conditions of the joints, muscles, and connective tissue, including autoimmune disease. They evaluate symptoms, apply the diagnostic criteria, and rule out conditions such as rheumatoid arthritis and lupus. They are also experienced with the WPI and SS scale.
The neurologist. May be involved when symptoms suggest a neurological condition. Numbness, tingling, severe headaches, or cognitive difficulties can overlap with nervous system disorders. Through imaging and nerve-related tests, a neurologist helps determine whether symptoms stem from fibromyalgia or another neurological condition.
The pain specialist. Pain management specialists focus on understanding and treating chronic pain. In fibromyalgia, they help identify the type of pain involved, often linked to altered pain processing in the nervous system. Their evaluation supports the diagnosis and guides long-term treatment aimed at reducing symptom severity and improving quality of life.
Because fibromyalgia presents with such a wide range of symptoms, no single specialist can assess every aspect. A multidisciplinary approach makes sure all possible causes are considered and the diagnosis is accurate. The process may take time, but it is essential for building an effective, personalized management plan.
When to Seek a Diagnosis
Knowing when to seek a diagnosis can make a real difference in how quickly you get the right support. Because the condition doesn’t show clearly on standard tests, many people delay seeking help or are told their symptoms aren’t serious. Certain patterns, though, strongly suggest a deeper evaluation is needed.
One of the most important signs is persistence. If you’ve had widespread pain, fatigue, or cognitive difficulties for more than three months, that is no longer temporary. Chronic symptoms that don’t improve with rest or basic treatment are a key indicator and shouldn’t be ignored.
Another critical factor is the effect on daily life. When symptoms begin to interfere with work, relationships, or simple routines, the condition is affecting overall function. Many people report trouble concentrating, finishing tasks, or keeping up energy through the day. That level of disruption warrants a thorough medical evaluation.
It’s also important to seek a diagnosis if tests keep coming back normal despite ongoing symptoms. This is common in fibromyalgia, since standard blood tests and imaging often fail to detect it. If you have persistent symptoms with no clear explanation, advocate for further assessment rather than letting the issue be dismissed.
Recognizing these signs early allows a more timely diagnosis. The sooner fibromyalgia is identified, the sooner you can begin managing symptoms and improving your quality of life.
Conditions That Look Like Fibromyalgia
Many conditions closely resemble fibromyalgia, which is a main reason diagnosis can be delayed or misunderstood. Because it shares widespread pain, fatigue, and cognitive difficulty with other disorders, doctors must carefully rule these out first. Knowing what can be mistaken for it clarifies why multiple tests and specialist evaluations are often needed.
Lupus. Systemic lupus erythematosus can cause fatigue, joint pain, and muscle aches that closely resemble fibromyalgia. But lupus is an autoimmune condition involving inflammation that can affect organs such as the kidneys, skin, and heart. Unlike fibromyalgia, it often shows abnormalities on blood tests, including specific antibodies. The distinction is critical because lupus needs a different treatment approach focused on controlling immune activity.
Rheumatoid arthritis. Both can cause joint pain and stiffness, but rheumatoid arthritis involves visible inflammation and joint damage over time, while fibromyalgia causes no structural joint damage. Imaging and lab tests for inflammatory markers help tell them apart.
Thyroid disorders. Hypothyroidism can mimic many fibromyalgia symptoms, including fatigue, muscle pain, and mental slowing. Because thyroid dysfunction affects metabolism and energy, the symptoms can feel very similar. Blood tests of thyroid hormone levels are essential to rule it out first.
Multiple sclerosis. MS may resemble fibromyalgia, especially when symptoms include fatigue, numbness, tingling, and cognitive changes. But MS involves nervous system damage that can be seen on imaging such as MRI, while fibromyalgia produces no structural neurological damage.
Because these conditions overlap, distinguishing them from fibromyalgia is a crucial step. Each has a different underlying cause and needs a different treatment strategy.
Accurate diagnosis ensures patients get appropriate care and avoid unnecessary or ineffective treatment, which is why thorough evaluation, including lab tests and clinical assessment, is essential.
What Happens After a Diagnosis
Receiving a diagnosis can feel overwhelming, but it also brings clarity and direction. Once the condition is identified, the focus shifts from searching for answers to managing symptoms and improving daily function.
Treatment is typically individualized, since symptoms vary widely. Rather than a single solution, management usually combines approaches targeting pain, fatigue, sleep, and overall well-being. Medication may be used in some cases, but lifestyle strategies often matter just as much.
One of the most important parts is building a sustainable daily routine: consistent sleep, gentle physical activity, and pacing energy through the day. These habits help stabilize the nervous system and reduce flare-ups.
Lifestyle changes also extend to diet and stress management. Many people find that cutting back on processed foods, staying hydrated, and managing stress noticeably affects how their symptoms fluctuate. Small, consistent changes often bring real improvement over time.
Long-term management aims for balance rather than eliminating symptoms. The condition may not fully disappear, but many people learn to reduce its impact and regain control of daily life. With the right strategies and support, it’s possible to live more comfortably and keep a stable level of function.
Can Fibromyalgia Be Misdiagnosed?
Yes, and more often than many people realize. With no single definitive test, diagnosis relies heavily on symptom patterns and excluding other conditions, which makes it vulnerable to both underdiagnosis and misinterpretation.
A common problem is confusion with conditions that share symptoms. Lupus, rheumatoid arthritis, thyroid dysfunction, and even neurological disorders can cause fatigue, widespread pain, and cognitive difficulty. If these aren’t carefully ruled out, fibromyalgia may be missed or wrongly diagnosed.
Another major reason is overlap with mental health conditions. Since fibromyalgia often coexists with anxiety or depression, some symptoms may be blamed entirely on psychological causes. Mental health plays a role, but it doesn’t fully explain the physical and neurological aspects of the condition.
Inconsistent symptoms add to the challenge. They can vary from day to day, creating uncertainty during evaluations. On milder days, symptoms may look minor, making it harder to capture the full severity.
Because of all this, patients are often diagnosed only after a long process of elimination. That’s why it’s important to see experienced providers who understand the condition’s complexity and use updated criteria.
Fibromyalgia Diagnosis Checklist
If you suspect fibromyalgia, this checklist can help you recognize common patterns. It isn’t a diagnostic tool, but it reflects the key features doctors look for.
- Persistent widespread pain across multiple areas of the body
- Ongoing fatigue that doesn’t improve with rest
- Cognitive difficulties such as poor concentration or memory problems
- Non-restorative sleep or waking up unrefreshed
- Normal or inconclusive lab results despite ongoing symptoms
When several of these are present together for an extended period, they may point to fibromyalgia and should be evaluated by a healthcare professional.
FAQs
Why do fibromyalgia tests often come back normal?
Because fibromyalgia doesn’t cause visible damage to tissues or organs. It affects how the nervous system processes pain, which standard blood tests and imaging can’t detect.
Can you have fibromyalgia without pain everywhere?
Yes. In early or milder cases, pain may not be present in every area at once. Over time, though, it typically becomes more widespread, which is a key feature used in diagnosis.
How do doctors rule out fibromyalgia?
They don’t directly rule it out. They rule out other conditions first. Once other causes are excluded and the clinical criteria are met, fibromyalgia can be diagnosed.
What is the fastest way to diagnose fibromyalgia?
There is no instant test. The most efficient route is a thorough symptom evaluation using current criteria, combined with targeted tests to exclude other conditions.
Conclusion
Diagnosing fibromyalgia isn’t straightforward, which is what makes it so challenging for patients and providers alike. The tests matter, but they often focus on ruling out other conditions rather than identifying fibromyalgia itself. That gap can leave people uncertain, especially when their symptoms are real but hard to measure with traditional methods.
Understanding how these tests work, and what they may miss, brings valuable clarity. It shows why fibromyalgia calls for a broader approach that considers symptom patterns, patient history, and nervous system sensitivity rather than relying only on lab results.
If you have ongoing symptoms that fit fibromyalgia, recognizing this diagnostic complexity is an important step. With the right knowledge, persistence, and medical support, it becomes easier to move toward an accurate diagnosis and a management plan that truly addresses your condition.